

Chronic Lymphocytic Leukemia (CLL)
Compliance rules
1Abstract
Chronic lymphocytic leukemia (CLL) is the most common form of leukemia in Central Europe. CLL is clinically and biologically heterogeneous. The median age at diagnosis is 70 years, with a wide age range. The disease may be preceded by monoclonal B-cell lymphocytosis (MBL).
Antineoplastic treatment is initiated only when symptoms appear. The choice of medication depends on the patient’s general condition, relevant comorbidities, and genetic alterations in the CLL cells. Treatment has evolved; instead of the previous standard of chemoimmunotherapy, targeted inhibitors that interfere with B-cell receptor signaling or the regulation of programmed cell death are now used as the standard of care. The optimal combinations and sequences of the various CLL therapies currently available have not yet been definitively established.
2Basics
2.1Definition and Basic Information
The WHO classification describes CLL as an indolent (lymphocytic) B-cell lymphoma characterized by a leukemic course. In contrast to previous versions, B-PLL is no longer recognized as a separate entity in the current 5th edition of the WHO classification (WHO-HAEM5) from 2022 and has been integrated into other entities (prolymphocytic variant of CLL (>15% prolymphocytes), variant of mantle cell lymphoma, splenic B-cell lymphoma/leukemia with prominent nucleoli) [1]. Small lymphocytic lymphoma (SLL) is a B-cell lymphoma that exhibits the same histological and immunophenotypic characteristics as CLL but primarily manifests in lymph nodes, the spleen, or other lymphoid organs, whereas peripheral blood shows no or only minimal involvement (<5,000 clonal B lymphocytes/µl). In the 2022 WHO classification, SLL and CLL are considered a single entity, and the same treatment recommendations apply to SLL as to CLL.
2.2Epidemiology
CLL is the most common leukemic disease in Western industrialized countries. According to current data from the United States (SEER-21 Registry), the age-adjusted incidence of CLL was 4.6 per 100,000 inhabitants per year. Approximately 0.6% of people develop CLL during their lifetime. The median age at diagnosis was 70 years. Only about 2.0% of patients with CLL were younger than 45 years at the time of diagnosis. Men were affected more frequently (M:F 1.9:1) [2].
While the incidence of CLL has remained stable over the past two decades, mortality has declined. The 5-year relative survival rate for CLL cases was 65.1% in 1975 and improved to 90.2% between 2016 and 2022 [2]. While similar epidemiological data have been reported in Europe, the incidence is lower among Asian populations [3, 4].
2.3Pathogenesis
CLL has a characteristic immunophenotype but is biologically and clinically heterogeneous. Central elements of its pathogenesis include the inhibition of apoptosis and the dysregulation of proliferation. Genomic analyses have led to the identification of numerous genetic aberrations and, increasingly, to the differentiation of clinically relevant subgroups with distinct signaling pathways [5, 6].
The B-cell receptor signaling pathway is of particular importance, as the blockade of critical kinases, including BTK and PI3K, can be exploited therapeutically. BCL2-dependent signaling pathways play a role in the apoptotic defect observed in CLL, and BH3 mimetics are therefore therapeutically effective.
However, the growth and circulation of CLL cells are controlled not only by cell-intrinsic signals but also by interactions with the microenvironment [7].
2.4Risk Factors
The risk of developing CLL is increased by the following factors:
Acquired Factors
According to the German Occupational Diseases Ordinance (No. 1318), exposure to organic solvents, such as benzene, may be considered a risk factor [8]. However, robust evidence for this or for the significance of other acquired risk factors is currently lacking.
Hereditary factors
First-degree relatives of CLL patients have an 8.5-fold increased risk of developing CLL and a 1.9- to 2.6-fold increased risk of developing another indolent lymphoma [9, 10]. However, due to the low incidence of these lymphoid neoplasms, the absolute risk of developing the disease among relatives remains low.
A small group of patients comes from families with a strikingly high incidence of CLL and other indolent lymphomas [9, 10]. The genetic basis of this predisposition is not fully understood [10].
CLL is preceded by a mostly undiagnosed, clinically asymptomatic precursor stage characterized by the proliferation of clonal B cells. These cells exhibit the biological characteristics of CLL cells and are referred to as monoclonal B-cell lymphocytosis (MBL); see Onkopedia entry on Monoclonal B-Cell Lymphocytosis (in German only). MBL is detectable in >5% of people over the age of 60. The risk of progression to CLL requiring treatment is approximately 1% per year [11]. It depends on the number of monoclonal B lymphocytes and molecular characteristics such as the IGHV mutation status [12, 13].
3Prevention and Early Detection
There is no evidence of effective measures for preventing CLL. Early detection based on the identification of monoclonal B-cell lymphocytosis has not been established. It would only be useful if early diagnosis of CLL led to a significant improvement in prognosis. Within the framework of the DCLLSG’s CLL12 protocol, no added benefit was observed for early intervention with the BTK inhibitor ibrutinib in patients with risk factors in early-stage Binet A compared to a “watch and wait” strategy [14].
4Clinical characteristics
The disease is characterized by lymphocytosis, which is often discovered incidentally. As the disease progresses, lymphadenopathy, splenomegaly, hepatomegaly, signs of bone marrow failure, and possibly autoimmune cytopenias may occur. Clinical symptoms may manifest primarily as B-symptoms and an increased susceptibility to infection.
5Diagnosis
5.1Criteria
According to the criteria of the 2018 International Workshop on CLL (iwCLL), the diagnosis of CLL is defined by the fulfillment of the following criteria [15]:
Detection of at least 5,000 clonal B-lymphocytes per μl of peripheral blood over a period of at least three months. Below this threshold, monoclonal B-cell lymphocytosis (MBL) may be diagnosed if there are no signs of disease (B-symptoms, lymphadenopathy, hepatomegaly, splenomegaly, cytopenia, etc.).
Predominance of small, morphologically mature-appearing lymphocytes in the cytological examination of the blood smear.
Co-expression of the B-cell antigens CD19 and CD23 with the T-cell antigen CD5 in multiparametric immunophenotyping. Another characteristic feature is the relatively weak expression of surface immunoglobulin, CD20, and CD79b. The monoclonality of the lymphocytes can be demonstrated by light-chain restriction (Igκ or Igλ), preferably through dual labeling of CD19/Igκ or CD19/Igλ.
Characteristic findings from microscopy, immunophenotyping, and genetics are presented in the Chronic Lymphocytic Leukemia knowledge database and in the eLCH—eLearning Curriculum in Hematology for bone marrow cytology using virtual microscopy (https://ehaematology.com/).
5.2Diagnosis
The diagnostic approach depends on the primary set of findings, typically characterized by the key finding of lymphocytosis with or without accompanying lymphadenopathy. If CLL is suspected, the following tests are recommended; see Table 1 and Table 2.
5.3Classification (Staging)
For staging according to Binet (the more commonly used system in Europe; see Table 3) [16] or Rai [17], only a physical examination and a complete blood count are required. The assessment of the five possible affected lymph node regions (neck, axilla, groin, spleen, liver; e.g., for staging according to Binet) is primarily performed by palpation. The results of imaging studies (organomegaly on ultrasound, CT) are not relevant for staging, even though in individual cases a lymphoma mass (e.g., mediastinal, retroperitoneal) may be relevant to treatment.
Stage | Definition |
|---|---|
A | Hemoglobin ≥10 g/dl Platelets ≥100,000/µl <3 affected regions2 (LK1 , liver, or spleen) |
B | Hemoglobin ≥10 g/dl Platelets ≥100,000/µl 3 or more affected regions2 (lymph nodes1 , liver, or spleen) |
C | Hemoglobin <10 g/dl Platelets <100,000/µl |
2 The regions (n=5) include cervical, axillary, and inguinal lymph node enlargements (unilateral or bilateral), as well as liver and spleen enlargements (detected only by physical examination).
5.4Prognostic Factors
Among the biological prognostic factors (Chapter 5.2, Table 2), TP53 aberrations (17p13 deletion [FISH] and TP53 mutation [Sanger sequencing or NGS]), the mutation status of the variable segments of the immunoglobulin heavy chain genes (IGHV), and the complex karyotype are prognostically relevant (Table 2). The significance of serum β2-microglobulin as a prognostic factor in the context of targeted therapies has somewhat diminished. Other biomarkers, such as SF3B1/NOTCH1 mutations and other genomic aberrations, require further prospective validation and currently do not form the basis for specific therapeutic considerations outside of clinical trials. Their routine testing is not indicated outside of clinical trials.
To better assess the prognosis before initiating first-line therapy, the CLL-IPI (International Prognostic Index) can be calculated using the following parameters (https://www.qxmd.com/calculate/cll-ipi): age (≤/> 65 years), Binet stage, β2-microglobulin (</>3.5 mg/dl), IGHV mutation status, 17p13 deletion (FISH), and TP53 mutation status [18]. This prognostic index was developed based on immunochemotherapy. It retains its value for assessing progression-free survival (PFS) in the context of targeted therapies, but not for overall survival (OS). The CLL-IPI therefore does not influence the choice of first-line therapy [19].
5.5Differential Diagnoses
The most important differential diagnoses are:
Monoclonal B-cell lymphocytosis (for the risk of progression to CLL, see Onkopedia: Monoclonal B-cell Lymphocytosis (in German only)).
Small lymphocytic lymphoma (SLL): Nodal, non-leukemic lymphoma (<5,000 clonal B cells/µl) with the microscopic and immunophenotypic profile of CLL
Reactive forms of lymphocytosis (viral infections, collagenoses).
Other indolent lymphomas with a leukemic course (follicular lymphoma—see Onkopedia Follicular Lymphoma (in German only); lymphoplasmacytic lymphoma—see Onkopedia Waldenström’s Disease (in German only)/ Lymphoplasmacytic Lymphoma; marginal zone lymphomas—see Onkopedia Marginal Zone Lymphoma (in German only); mantle cell lymphoma—see Onkopedia Mantle Cell Lymphoma).
Hair cell leukemia (see Onkopedia Hairy-Cell Leukemia).
Particular attention must be paid to distinguishing this condition from mantle cell lymphoma due to the similar immunophenotype with coexpression of CD19 and CD5; however, unlike CLL, mantle cell lymphomas are usually negative for CD23. In cases of CLL with a non-classical immunophenotype, a FISH analysis to rule out the typical aberration of mantle cell lymphomas—i.e., the (11;14) translocation—or a histological examination is indicated.
In patients with rapidly progressive lymphadenopathy or severe B-symptoms, a Richter transformation should be ruled out via biopsy at any stage of the disease. A PET-CT scan is useful for detecting the most likely site of transformation and for selecting the optimal location for a tissue biopsy.
6Treatment
6.1Treatment structure
Treatment is generally indicated in Binet stage C, as well as in Binet stages B or A, if additional criteria for mandatory treatment are met (“active disease” according to iwCLL criteria [15]):
Onset or worsening of anemia or thrombocytopenia.
Massive (>6 cm below the costal margin), progressive, or symptomatic splenomegaly; note: spleen size varies individually depending on height and weight.
Massive (>10 cm in diameter), progressive, or symptomatic lymphadenopathy.
Lymphocyte doubling time of less than 6 months or a 50% increase in 2 months, starting from a baseline value of at least 30,000 lymphocytes/µl, and after exclusion of other causes of lymphocytosis.
Autoimmune cytopenia refractory to standard therapy (corticosteroids).
One of the following constitutional symptoms:
unintentional weight loss >10% in 6 months
Fever >38°C of unknown cause lasting more than 2 weeks
Night sweats lasting more than one month without evidence of infection
severe fatigue
The treatment structure for first-line therapy is shown in Figure 1, and that for relapse therapy in Figure 3.
The choice of therapy for CLL is guided by specific comorbidities (particularly cardiac and renal diseases), concomitant medications (especially anticoagulation), the patient’s preferences (intravenous versus oral therapy, frequency of follow-up visits), and the molecular and cytogenetic status, rather than chronological age (Figure 2). Whenever possible, therapy should be administered within the framework of clinical trials.
The vertical ranking of the individual treatment options shown (Figures 1 and 3) reflects a prioritization that is not always supported by direct comparative, randomized Phase III trials with the highest level of evidence. In this respect, it primarily represents a preliminary recommendation from the expert panel, one that is currently supported by the majority of experts. Additional decision-making factors, such as the individual comorbidity profile, adherence considerations, the effort required for administration and the logistics of the therapeutic intervention, and, above all, patient preference, should be taken into account when making the final treatment decision (Figure 2).
The standard dosages for all therapies are based on data from multicenter studies. In cases of advanced age or comorbidity, a dose reduction may be necessary on a case-by-case basis, or (more commonly) during the course of therapy to accommodate individual side effects. For patients on multiple medications, attention must be paid not only to potentially limited compliance but also to the possible occurrence of drug interactions.
1 active disease according to the 2018 IWCLL criteria [15];
2 watch and wait—a wait-and-see approach;
3 BSC – best supportive care
4 The sequence of the following therapies represents one possible approach (see Chapter 6.1.1.1, Chapter 6.1.1.2, and Chapter 6.1.1.3).
Based on the current data, this sequence is not mandatory. The individual comorbidity profile, adherence considerations, the effort required for administration and the logistics of the therapeutic intervention, as well as the patient’s preference, should be taken into account when determining the final treatment plan.
5 In cases where acalabrutinib, zanubrutinib, or pirtobrutinib are contraindicated or unavailable, ibrutinib (+/- obinutuzumab) remains a treatment option, provided that the risk of increased cardiac side effects is taken into account. Acalabrutinib, zanubrutinib, and pirtobrutinib have not been systematically evaluated in younger or fit patients as first-line therapy.
6 When using I+V, cardiac toxicity must be carefully weighed, particularly in older patients.
7 When using AV plus obinutuzumab, the risk of infectious complications must be weighed, particularly in older patients.
8 When using the ncBTKi pirtobrutinib, it should be noted that there is currently insufficient evidence regarding follow-up therapies, including the subsequent use of cBTKi in cases of relapse.
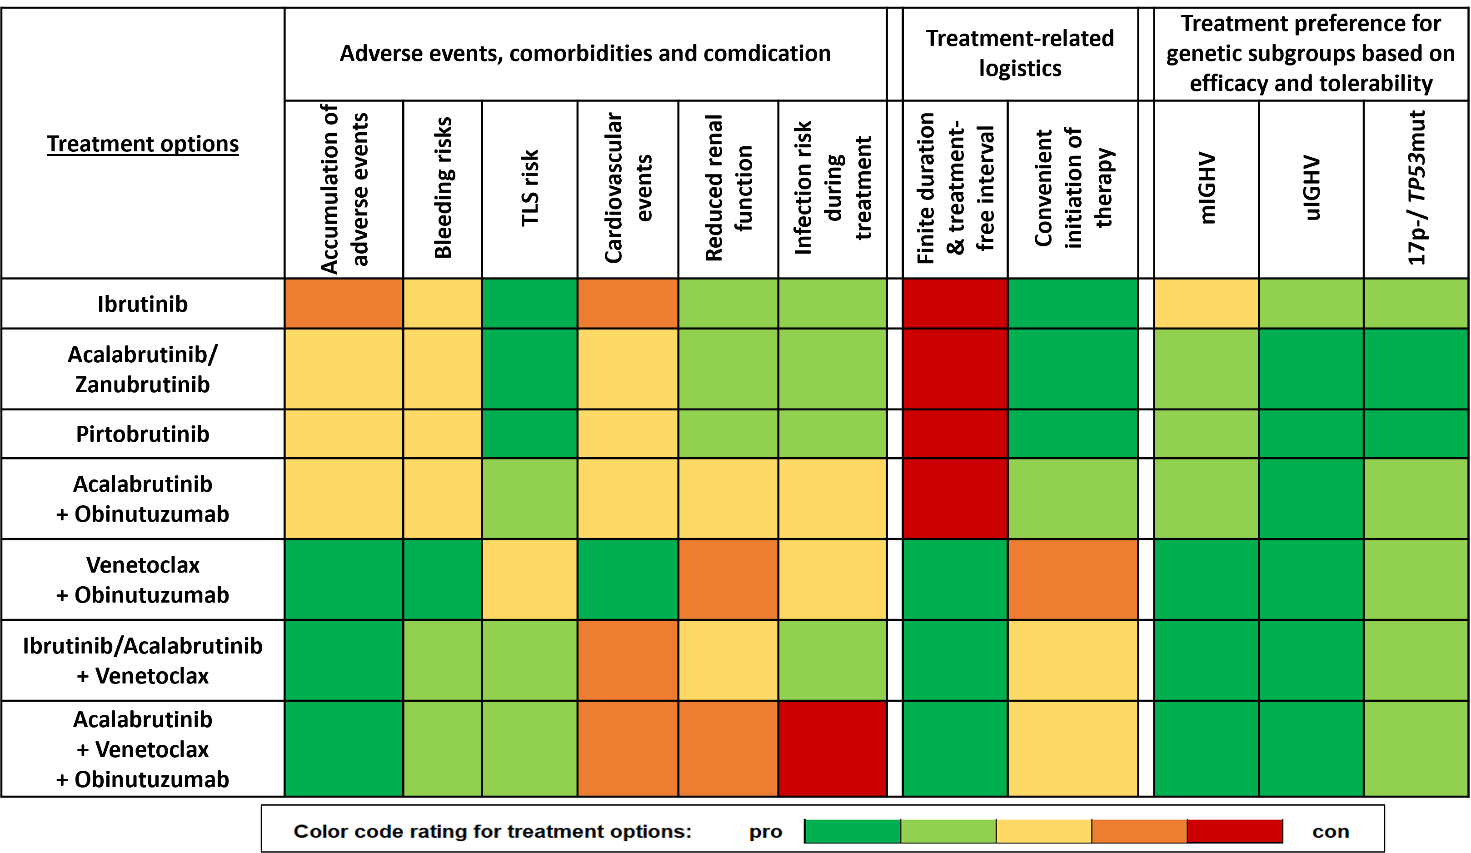
(Color scale corresponding to recommendation strength: dark green = very strong, light green = strong, yellow = intermediate, orange = weak, red = very weak)
*modified from [20]
6.1.1First-line therapy
Treatment options for first-line therapy are currently changing and expanding. The following are currently considered genetic risk factors:
del(17p13) or TP53 mutation
IGHV unmutated status (IGHVunmut )
Various treatment options are available, particularly for patients without a high-risk genetic profile (without del(17p13) or TP53 mutation). The selection of these options—which are generally chemotherapy-free—is primarily guided by existing comorbidities or potential organ toxicity (particularly renal or cardiac) as well as possible interactions with medications already prescribed independently of CLL. The relevant results from treatment studies can be summarized as follows:
BTK inhibitors (BTKIs) as monotherapies or in combination with monoclonal anti-CD20 antibodies
The BTKi ibrutinib resulted in a significant prolongation of both progression-free survival (hazard ratio (HR) 0.16; median not reached) and overall survival (HR 0.16; median not reached), as well as a significant increase in the remission rate (86% vs. 35%) (RESONATE-2 study) [19].
In the E1912 study, ibrutinib/rituximab, compared with fludarabine/cyclophosphamide/rituximab (FCR), resulted in patients ≤70 years of age (younger and fit patients) resulted in a significant prolongation of progression-free survival (HR 0.352) and overall survival (HR 0.168), with the benefit primarily attributable to ibrutinib, as subsequent comparative studies could not demonstrate an advantage of adding rituximab to ibrutinib over ibrutinib monotherapy [21]. Therefore, the combination of ibrutinib plus rituximab is recommended only to a limited extent.
In the ALLIANCE trial (a randomized comparison of bendamustine plus rituximab (BR) with ibrutinib monotherapy or ibrutinib/rituximab), ibrutinib resulted in a significant prolongation of progression-free survival (HR 0.39) compared with BR in patients ≥65 years to a significant prolongation of progression-free survival (HR 0.39), but—not least due to increased toxicity—not to overall survival, albeit with a still relatively short follow-up period [22]. Furthermore, the combination of ibrutinib and rituximab shows no advantage over ibrutinib monotherapy. Therefore, ibrutinib is generally recommended as monotherapy, and by analogy, also for younger, fit patients.
No data from randomized trials are available for the combination of ibrutinib and obinutuzumab in fit patients under 65 years of age. Approval was granted based on data from older patients and patients with comorbidities; see chapter 6.1.1.1.1. The EU approval also covers younger patients (see corresponding recommendation in Figure 1).
To date, there are no data from randomized trials for the second-generation BTKi acalabrutinib, either as monotherapy or in combination with obinutuzumab, in fit patients under 65 years of age. Approval based on the ELEVATE-TN trial (comparison of acalabrutinib monotherapy with acalabrutinib/obinutuzumab or chlorambucil/obinutuzumab) [23] was granted based on data from older patients and patients with comorbidities. The EU approval also covers younger patients (see Figure 1 for the corresponding recommendation). Furthermore, over a longer follow-up period (5-year update), the CR/CRi rate in the acalabrutinib and obinutuzumab arm was 37% for acalabrutinib/Obi versus 14% for chlorambucil/Obi, which translates into a benefit in PFS and overall survival compared with chlorambucil/obinutuzumab [24].
In the ELEVATE-RR recurrence study, acalabrutinib was shown to have a more favorable toxicity profile than ibrutinib in a direct comparison, while maintaining equivalent efficacy (in particular, a significantly reduced risk of hypertensive events and atrial fibrillation/flutter).
No data from randomized trials in fit patients under 65 years of age are currently available for the second-generation BTKi zanubrutinib. Based on the SEQUOIA study (first-line therapy in patients aged ≥65 years, a randomized comparison of zanubrutinib and BR), zanubrutinib received EU approval for CLL in November 2022 (regardless of performance status and age, for both first-line and cases of relapse). In this study, significantly improved progression-free survival was documented compared with first-line therapy with bendamustine/rituximab [25].
In a relapse study (ALPINE Trial), a direct comparison of zanubrutinib and ibrutinib demonstrated higher efficacy (PFS and overall response rate) along with an improved toxicity profile in favor of zanubrutinib with regard to cardiac events (atrial fibrillation/atrial flutter). Additionally, this Phase III study also demonstrated improved PFS with zanubrutinib compared to ibrutinib (3-year PFS 64.9% vs. 54.8%) [26, 27].
By analogy with the data from the relapse studies (ALPINE, ELEVATE-RR), a reduced toxicity profile is also assumed for zanubrutinib and acalabrutinib in first-line therapy. Accordingly, both agents are recommended as preferred alternatives to ibrutinib when initiating first-line therapy. In the ELEVATE-RR study, acalabrutinib demonstrated a significantly reduced rate of hypertensive events; however, unlike zanubrutinib, it is associated with an increased rate of headaches during the first weeks of therapy.
However, patients already undergoing first-line therapy with ibrutinib without relevant side effects should not be switched to acalabrutinib or zanubrutinib, as—based on current study data—there are no differences in overall survival between these two agents and ibrutinib.
Since August 2026, the ncBTKi pirtobrutinib has also been approved in the EU for first-line treatment of CLL, based on the BRUIN-313 and -314 studies. In the BRUIN-313 study, pirtobrutinib demonstrated a significant prolongation of progression-free survival (PFS) and a substantial reduction in risk compared with the standard therapy, bendamustine [28]. The BRUIN-314 study further demonstrated the non-inferiority of pirtobrutinib compared to ibrutinib in terms of overall response rate, while also showing a more favorable safety profile and fewer cardiac side effects [29]. Despite the high efficacy and safety of the ncBTKi pirtobrutinib, even in first-line therapy, it must be noted that, on the one hand, the follow-up period for the aforementioned first-line studies is still short, and, on the other hand, there are currently no reliable data available regarding relapse therapy following failure of pirtobrutinib — that is, whether, among other things, cBTKIs are effective following exposure to an ncBTKi.
Time-Limited Combination Therapies
In general, particularly for patients with a long life expectancy and no high-risk features, a time-limited combination therapy — i.e., one containing venetoclax — should be preferred, provided that other factors (e.g., renal function, susceptibility to infection, travel to the treatment center) allow for it.
BCL2 inhibitor venetoclax in combination with monoclonal anti-CD20 antibodies
If long-term therapy is not desired or if BTKi therapy is considered unsuitable (dual antiplatelet therapy, severe bleeding tendency, ventricular arrhythmias, or possibly severe heart failure), a time-limited therapy based on venetoclax/obinutuzumab (see below) should be chosen as an alternative.
Venetoclax plus obinutuzumab (Venetoclax/Obinutuzumab, VenObi) was approved based on studies in older patients or those with comorbidities. The time-limited combination therapy consisting of the BCL2 inhibitor venetoclax (12 cycles) plus obinutuzumab (6 cycles) proved significantly superior to chemoimmunotherapy with chlorambucil/obinutuzumab in terms of progression-free survival in the CLL14 study (hazard ratio 0.35; median not reached) [30, 31]. After a median follow-up of 65.4 months, no difference in overall survival has been observed to date when comparing the two treatment arms [32].
Overall, VenObi represents a highly effective yet time-limited (12 cycles; planned treatment duration of approximately 11 months) treatment option for first-line therapy. Patients with a mutated IGHV status benefit the most from this combination therapy; consequently, a primary recommendation is made for this low-risk group regarding VenObi—due to the limited duration of treatment, in contrast to continuous BTKi therapy.
Due to its favorable side effect profile, VenObi also proves to be a suitable treatment option for patients with a high cardiac risk profile (particularly those with a history of severe arrhythmias). However, VenObi may only be used in exceptional cases in patients with impaired renal function (creatinine clearance <30 mL/min and >15 mL/min) due to a significantly increased risk of tumor lysis syndrome (contraindicated for creatinine clearance below 15 mL/min).
In the DCLLSG’s CLL13 study (a randomized comparison of FCR/BR vs. venetoclax/rituximab vs. VenObi vs. venetoclax/obinutuzumab/ibrutinib), a significant advantage of VenObi in terms of progression-free survival compared to chemoimmunotherapy (FCR, BR) as well as a descriptive advantage over venetoclax/rituximab in younger/fit patients [33]. VenObi therefore also represents a good, temporary treatment option for young/fit patients with a favorable risk profile (IGHVmut, no TP53 aberration, no complex karyotype). Furthermore, the triple combination of VenObi + ibrutinib proved superior to the VenObi combination in terms of prolonging PFS. However, given the lack of a difference in overall survival on the one hand and the higher incidence of adverse effects (including the occurrence of secondary neoplasms) on the other, this combination is not recommended for routine use and is not approved.
In the interim analysis of the CLL17 study, which also included high-risk patients with TP53 aberrations and/or a complex karyotype, the VenObi regimen was shown to be non-inferior to continuous BTKi therapy with ibrutinib, although follow-up was still limited (34 months) [34]. However, descriptive subgroup analyses revealed slightly less favorable PFS rates compared to continuous ibrutinib therapy in high-risk subpopulations (unmutated IGHV, TP53 aberration, complex karyotype).
Ibrutinib plus Venetoclax
Ibrutinib/venetoclax (I+V) was approved in August 2022 based on a Phase III trial (GLOW trial), which demonstrated superior PFS and OS with I+V compared to a combination of chlorambucil plus obinutuzumab in older and/or comorbid patients [35]. However, it is important to note the significant toxicity of this combination in this specific patient population, as reflected, for example, by a 14% rate of atrial fibrillation. In addition, data from another study (the Phase II CAPTIVATE study), which also included fit patients, were used as the basis for approval. In this study, a good response was also documented in patients with high-risk features (particularly those with unmutated IGHV status) [36]. In the CLL17 study, which also included high-risk patients with TP53 aberrations and/or a complex karyotype, the I+V regimen was shown to be non-inferior to long-term BTKi therapy with ibrutinib; however, the follow-up period of 34 months was still insufficient to draw definitive conclusions [34]. The slightly less favorable PFS rates observed for VenObi compared to continuous ibrutinib therapy in descriptive subgroup analyses among high-risk subpopulations (unmutated IGHV, TP53 aberration, complex karyotype) were less evident in the I+V arm.
By administering ibrutinib monotherapy over 3 cycles followed by the approved I+V combination over 12 cycles, the risk of tumor lysis syndrome was reduced, allowing the (entirely oral) therapy to be administered on an outpatient basis in most cases. Particularly for younger patients with a mutated IGHV status who desire a time-limited, fully oral therapy, I+V represents a highly effective treatment option, albeit one limited to 15 cycles (approximately 14 months). Data are now also available on relapse following I+V treatment, which, on the one hand, show no evidence of the development of BTK or PLC-ɣ resistance mutations and, on the other hand, suggest that retreatment with BTK inhibitors is effective [37].
Acalabrutinib plus venetoclax ± obinutuzumab (AV or AVO):
The EMA approved acalabrutinib/venetoclax (A+V) ± obinutuzumab (AVO) in June 2025 based on a Phase III trial (the AMPLIFY trial). In this study, significantly better PFS was demonstrated in younger/fit patients without TP53 aberrations compared to chemoimmunotherapy (FCR/BR) [38]. In particular, patients with an unmutated IGHV status benefited in terms of PFS from the addition of obinutuzumab (AVO regimen). In addition, patients on AV also showed better overall survival compared to chemoimmunotherapy. The AVO regimen was associated with an increased incidence of severe, sometimes fatal, infectious complications (the study was conducted during the COVID-19 pandemic), so that, unlike the AV regimen, no survival benefit was observed for AVO compared to chemoimmunotherapy. AV and AVO are therefore recommended as temporary therapies, analogous to I+V, particularly for low-risk (IGHV-mut) patients and those with intermediate risk (IGHV-unmut). Data on high-risk patients (TP53 aberration) are not available based on the AMPLIFY study, as this patient group was excluded from the study.
6.1.1.1Favorable genetic risk profile (mutated IGHV status, no del(17p13)/TP53 mutation, no complex karyotype)
In summary, in patients with a favorable genetic risk profile (IGVHmut, no TP53 mutation, no complex karyotype), a time-limited regimen of venetoclax/obinutuzumab (12 cycles) should be the preferred treatment. With the same level of recommendation, a time-limited, entirely oral regimen based on ibrutinib plus venetoclax or, alternatively, acalabrutinib plus venetoclax is recommended as first-line therapy, particularly for younger patients without concomitant cardiac conditions. The data available for the AV combination are even more limited (only one Phase 3 study—AMPLIFY—with a short follow-up period). In cases of severely impaired renal function (GFR < 30 mL/min) or if a purely oral regimen is desired, or if there are logistical and/or biological issues regarding the venetoclax titration phase, first-line therapy with a second-generation BTK inhibitor—acalabrutinib or zanubrutinib—as long-term oral therapy should be considered in this patient population. It should be noted that ibrutinib exhibits increased cardiotoxicity compared to second-generation BTK inhibitors (see the ALPINE and ELEVATE-RR relapse studies) and also compared to pirtobrutinib (see the BRUIN-314 first-line study); therefore, ibrutinib monotherapy is now recommended only to a limited extent. In cases of severe cardiac comorbidities (including ventricular extrasystoles), venetoclax/obinutuzumab is the preferred treatment, whereas in cases of significant renal impairment (creatinine clearance <70 mL/min), BTKi-based therapy should be preferred (Figure 1).
6.1.1.1.1Poor general condition (frail patients, “no go”)
For patients in very poor general condition and with a short life expectancy due to comorbidities or general frailty not related to CLL, supportive care is the first priority. In selected cases, however—not least based on the so-called FRAIL study—a therapeutic trial with BTKi-based monotherapy, particularly with acalabrutinib, may be attempted. In the FRAIL study, acalabrutinib was shown to improve general condition and, consequently, frailty per se [39].
6.1.1.2Intermediate Genetic Risk (unmutated IGHV status, no del(17p) or TP53 mutation, no complex karyotype)
For patients with an unmutated IGHV status and no other genetic risk factors (no TP53 aberration), the treatment options described in chapter 6.1.1.1 are available. The selection of treatment options—which are generally chemotherapy-free—is primarily based on existing comorbidities (particularly renal or cardiac), potential organ toxicity, and possible interactions with medications already prescribed independently of CLL.
Summary of Available Data
Based on favorable Study Results, continuous therapy using second-generation BTK inhibitors (acalabrutinib ± obinutuzumab; zanubrutinib), the ncBTKi pirtobrutinib, or a time-limited regimen with ibrutinib plus venetoclax, acalabrutinib plus venetoclax (with obinutuzumab if necessary), or venetoclax plus obinutuzumab (Figure 1). Long-term therapy with the ncBTKi pirtobrutinib is also possible in this situation; however, it is not recommended as a priority due to the lack of evidence regarding potential follow-up therapies.
Continuous therapy with acalabrutinib could be combined with obinutuzumab in this subgroup, as the 6-year follow-up of the ELEVATE-TN study showed a clear difference in PFS (75% vs. 60%)—albeit no significant difference in OS—compared with acalabrutinib monotherapy [40]. Furthermore, within the ibrutinib arm of the E1912 study (comparison of ibrutinib/rituximab vs. FCR), no significant difference in PFS was observed between IGHV-mutated and IGHV-unmutated patients after a 4-year follow-up period. In contrast, other randomized trials (ALLIANCE, ILLUMINATE) with BTK inhibitors have shown reduced PFS in the group with unmutated IGHV. However, due to its cardiovascular toxicity profile (see chapter 6.1.1.1), treatment with ibrutinib monotherapy—unlike the second-generation BTK inhibitors acalabrutinib or zanubrutinib—is not recommended because of its cardiac toxicity profile, unless the patients are young and in good physical condition, have no pre-existing cardiac conditions, and second-generation BTK inhibitors are not available. Due to the short follow-up period and lack of data on relapse following failure of pirtobrutinib, pirtobrutinib is currently recommended as a second-line therapy after acalabrutinib or zanubrutinib. With time-limited treatment regimens such as venetoclax/obinutuzumab, ibrutinib plus venetoclax, or acalabrutinib plus venetoclax (with or without obinutuzumab), a significantly shorter PFS is observed in patients with unmutated IGHV status (compared to IGHVmut). However, the median PFS for patients with unmutated IGHV status after one year of therapy is more than 5 years, which translates to at least 4 years of treatment-free time for half of the patients. The longer time to the first PFS event with continuous BTKi therapy compared to time-limited venetoclax-based therapy does not indicate fundamental long-term superiority, since (although the evidence is limited) venetoclax-based treatment can be repeated in the event of relapse. In a randomized comparison (CLL17 study) between venetoclax/obinutuzumab and long-term BTKi therapy with ibrutinib (including patients with the unmutated CLL17 mutation), no significant difference in PFS or OS has been observed to date [34]. However, based on the CLL17 data, it is important to note the significantly increased risk of infection associated with the use of VenObi, particularly in older patients.
In cases of severe cardiac comorbidities (including ventricular extrasystoles), venetoclax/obinutuzumab is the preferred treatment regardless of IGHV status.
The combination of ibrutinib plus venetoclax (I+V) can also be used as a time-limited therapy (15 cycles) in patients with intermediate risk (IGHVunmut ). However, data from the GLOW study show a shorter PFS in the I+V arm for patients with IGHVunmut compared to the subgroup of patients with IGHVmut . However, the time to next treatment (TTNT) after I+V is approximately 20% at 5 years for both molecularly defined subgroups. For the combination based on acalabrutinib plus venetoclax, patients with IGHVunmut also showed a shorter 3-year PFS compared to the IGHVmut subgroup (69% vs. 86%), although this effect could be offset by the addition of obinutuzumab (AVO) (3-year PFS for AVO: IGHVmut 84% vs. IGHVunmut 83%). However, for this triple combination, the higher rate of potential infections — as described in the AMPLIFY study — must be taken into account, which then tends to result in a disadvantage for AVO in terms of OS. For this reason, this triple combination is recommended only for young, healthy patients with IGHVunmutor TP53 aberration who have no relevant history of infection and a good vaccination status, as a secondary option to the other options mentioned above, subject to a case-by-case decision.
Overall, it can therefore be concluded that for the group with intermediate genetic risk (IGHVunmut without concurrent evidence of high-risk genetics, such as a TP53 mutation or del(17p13)), based on current knowledge, continuous therapy with a BTKi or, alternatively, time-limited therapy in the form of VenObi, I+V, or AV can be recommended on an equal footing. The specific choice depends on individual patient characteristics (comorbidities, concomitant medications, patient preference, etc.).
6.1.1.3High genetic risk (del(17p), TP53 mutation, complex karyotype)
For CLL requiring treatment with del(17p13)/TP53 mutation or evidence of a complex aberrant karyotype, regardless of the patient’s general condition and after weighing efficacy and side effects, the continuous use of BTK inhibitors—primarily acalabrutinib, zanubrutinib, or, if appropriate, pirtobrutinib (ibrutinib is also a secondary option) is recommended. Since the follow-up periods for pirtobrutinib in BRUIN-313 and -314 are still short for this subgroup as well, and there is not yet sufficient experience regarding the recurrence situation following failure of pirtobrutinib, the use of pirtobrutinib is currently recommended as a secondary option to acalabrutinib or zanubrutinib. Alternatively, particularly in cases where BTK inhibitors are not suitable, the combination of venetoclax/obinutuzumab (over 12 cycles) or continuous venetoclax monotherapy may be used as first-line therapy; however, the CLL14 study demonstrated significantly worse PFS and overall survival for venetoclax/obinutuzumab compared to subgroups without TP53 mutations. In the CLL17 study as well, after 3 years of follow-up, the PFS data for patients with TP53 aberrations and/or a complex karyotype treated with VenObi were not statistically significantly inferior but were numerically worse compared with continuous therapy with ibrutinib [34]. In the CAPTIVATE study (Chapter 6.1.1.1.1), I+V also demonstrated a good response based on a small number of cases (n=27), although PFS was shorter than in patients without TP53 aberrations [35, 36]. With this caveat, I+V represents a valid treatment option for this high-risk population, provided there is a preference for a time-limited therapy. Formally, the combination of acalabrutinib plus venetoclax (+/- obinutuzumab; AV/AVO) is also approved for high-risk patients, even though the AMPLIFY approval trial had explicitly excluded patients with TP53 aberrations. Due to this limitation, AV or AVO cannot formally be recommended for patients with a high-risk profile (TP53 aberration, complex karyotype); however, it may be used in individual cases, as at least Phase II data are available for AVO [41].
Overall, for patients with a high-risk genetic profile, continuous therapy based on second-generation BTK inhibitors or, as a secondary option, the ncBTK inhibitor pirtobrutinib should be recommended, despite the currently limited data. Otherwise, time-limited therapies (particularly I+V; Ven/Obi, AV, or AVO are given lower priority) are also possible and approved based on individual patient characteristics.
6.1.2Second-line therapy
The choice of relapse therapy depends on several individual factors. In addition to the patient’s age and comorbidities, these primarily include clinical parameters such as the type of primary therapy, the duration of remission achieved, and any changes in the biological characteristics of CLL since the initial diagnosis in the context of clonal evolution (e.g., acquisition of a del(17p13) or TP53 mutation). Furthermore, after continuous therapy with BTK or BCL2 inhibitors, specific resistance mutations (including those in BTK, PLCγ2, or BCL2) may arise; detection of these mutations makes repeating the corresponding therapy appear inadvisable. Resistance testing can be particularly informative when using the non-cytotoxic BTK inhibitor (ncBTKi) pirtobrutinib following failure on acalabrutinib or zanubrutinib, as cross-resistance may occur. Testing for resistance mutations is also recommended in the reverse scenario—that is, prior to initiating a cytotoxic BTK inhibitor (cBTKi) following failure of the ncBTKi pirtobrutinib. However, the clinical significance of not all variants is clear. As a general rule, given the clear superiority of the new agents (particularly BTK and BCL2 inhibitors) over various chemoimmunotherapies in terms of overall survival (OS), the latter should now only be used in very select, exceptional cases of relapse (patient preference, pre-existing combined cardiac/renal conditions, etc.). If a patient has received chemoimmunotherapy as primary therapy, in the event of relapse — even with a long remission duration (>24 months) — repeat chemoimmunotherapy is not recommended due to the demonstrated survival benefit (e.g., the MURANO study) and the risk of secondary malignancies (including tMDS); instead, therapy with new agents is preferred. An algorithm is shown in Figure 3. Whenever possible, treatment should be conducted within the framework of clinical trials.
CR – complete remission; PD – progression; PR – partial remission; SD – stable disease: according to the 2018 IWCLL criteria [15], stable disease is considered treatment failure; BSC – best supportive care; alloSZT – allogeneic stem cell transplantation,
1 Early relapse: duration of remission less than 2 to 3 years; in cases of progression or early relapse, a Richter transformation should be ruled out using PET-CT and lymph node histology.
2 Late relapse: Duration of remission longer than 2 to 3 years.
3 In cases of contraindication to or unavailability of acalabrutinib, zanubrutinib, or pirtobrutinib, ibrutinib remains a treatment option, taking into account the increased risk of cardiac side effects
4 Discontinuation of idelalisib sales in Germany as of March 1, 2027
Patients who are refractory to current therapy or who achieve a remission duration of less than 3 years, as well as patients with relapsed disease who test positive for a del(17p13) or a TP53 mutation, have a poor prognosis. Before the introduction of the new agents, their median overall survival was 1–2 years, calculated from the start of salvage therapy. In these studies, achieving “stable disease” in patients requiring treatment, as defined by the 2018 IWCLL criteria, was also classified as treatment failure [15].
Meanwhile, the following agents are available: the covalent BTK inhibitors ibrutinib, acalabrutinib, and zanubrutinib; the non-covalently binding BTK inhibitor pirtobrutinib; the BCL2 inhibitor venetoclax (plus rituximab); and the PI3K-delta inhibitor idelalisib (plus rituximab). The registration trials primarily enrolled patients with relapse following chemoimmunotherapy; consequently, the data available on the use of these new agents in patients who have previously received BTK inhibitors or venetoclax-based regimens are limited.
The most important current study data can be summarized as follows, although it should be noted that in these studies, prior treatments were mostly based on chemoimmunotherapy, so the interpretive value regarding relapse therapy following targeted therapies is limited.
The BTK inhibitor acalabrutinib resulted in a significant prolongation of progression-free survival (HR 0.31) in patients who had received at least one prior therapy, compared with a treatment regimen chosen by the treating physician (idelalisib/rituximab or bendamustine/rituximab) (ASCEND study) [42].
The BTK inhibitor zanubrutinib resulted in a higher remission rate (80.4% vs. 72.9%, p=0.0264) and better 3-year PFS (64.9% vs. 54.8%) in patients with relapsed CLL compared with ibrutinib (ALPINE trial) [27]. In the subgroup of patients with TP53 aberrations, PFS was significantly better compared with ibrutinib (HR 0.53) [27].
The non-covalently binding BTK inhibitor pirtobrutinib was specifically tested in the BRUIN-321 study in patients who had all been pretreated with a covalent BTK inhibitor and, in half of the cases, also with venetoclax. Compared with relapse therapy using bendamustine/rituximab or idelalisib plus rituximab, pirtobrutinib demonstrated significantly better PFS (14 months vs. 8.2 months and 8.8 months, respectively). The time to next treatment (TTNT) was also significantly prolonged with pirtobrutinib (24 months vs. 10.9 months) [43].
The BCL2 inhibitor venetoclax, in combination with rituximab, resulted in prolonged PFS (HR 0.16; median not reached) and OS (HR 0.50; median not reached), an increase in the rate of hematologic remissions, and an increase in MRD negativity (MURANO study) [44, 45]. Venetoclax monotherapy resulted in a 79% remission rate in patients with relapsed or refractory CLL with evidence of del(17p13) or a TP53 mutation and following prior treatment with a BCR signaling pathway inhibitor (single-arm study) [46, 47].
The treatment recommendation for disease recurrence (see Figure 3) depends largely on the prior therapy:
For patients who have received first-line treatment with chemoimmunotherapy, BTK inhibitors are available as an alternative to the venetoclax/rituximab combination for second-line therapy. Results from direct comparative studies between venetoclax/rituximab and ibrutinib, acalabrutinib, or zanubrutinib are not available. Even though direct data from studies for this patient group are lacking, if a TP53 aberration is detected — even in the relapse — continuous therapy with a BTKi would, in principle, be preferred over a time-limited BCL2i-based treatment (VenR); conversely, in cases of mutated IGHV, there would be a preference for time-limited therapy with venetoclax/rituximab.
For patients who have received prior BTKi treatment, the combination of venetoclax and rituximab (VenR) represents the preferred standard of care starting with second-line therapy, regardless of risk classification or performance status, due to its high efficacy and limited treatment duration (2 years for VenR). Due to the clear superiority of VenObi over VenR in the first-line setting (see the DCLLSG’s CLL13 study), the VenObi regimen (as in the CLL14 study) can and should also be considered. Based on the EMA approval, pirtobrutinib may be administered regardless of prior therapies and, therefore, also in cases of relapse, regardless of whether prior therapy included a BTKi or venetoclax. For this specific treatment situation in particular, there is a stronger evidence base based on the BRUIN-321 study, which included 100% BTKIs-pretreated patients (in contrast to 3% BTKIs pretreatment in MURANO). Overall, even in the relapsed setting, the advantages and disadvantages of a time-limited regimen versus a continuous regimen — similar to first-line therapy — must be weighed and discussed with the patient.
Conversely, in patients who have previously been treated with venetoclax plus obinutuzumab, BTK inhibitors (cBTKi, ncBTKi) demonstrate very good efficacy. Following prior treatment with venetoclax plus obinutuzumab, re-treatment with venetoclax (plus rituximab, in accordance with the current approval) may be effective, particularly in cases of prolonged remission (over 2 to 3 years). Re-exposure to VenObi in relapse is currently being tested as part of the ReVenG study. However, there are currently insufficient data on how long the remission duration should be for re-treatment with the BCL2 inhibitor to be appropriate.
For patients who relapse after or during primary therapy based on ibrutinib plus venetoclax (I+V) or acalabrutinib plus venetoclax (AV, AVO), preliminary data are available on re-treatment with a BTKi or venetoclax-based therapy. In principle, therefore, only a preliminary recommendation can currently be made for relapse therapy based on BTK inhibitor monotherapy (including pirtobrutinib), venetoclax monotherapy, or venetoclax/rituximab.
In summary, following prior treatment with venetoclax/obinutuzumab and I+V, venetoclax-based therapy or a switch to a BTK inhibitor is possible. Conversely, following treatment failure—defined as disease progression—while on a covalent BTK inhibitor, therapy with venetoclax (+/- rituximab) or with the non-covalent BTK inhibitor pirtobrutinib may be initiated. If intolerance is the cause of first-line treatment failure, a switch to a different BTKi may be possible. When using BTK inhibitors, second-generation BTK inhibitors (acalabrutinib, zanubrutinib) and the non-covalent BTK inhibitor pirtobrutinib are preferred over first-generation BTK inhibitors ( ; zanubrutinib, see the ALPINE study) due to their more favorable side effect profile and, in some cases, greater efficacy; ibrutinib remains available as an alternative therapy. No definitive data on the optimal sequence are currently available.
6.1.2.1Additional recommendations in cases of disease progression or early relapse (less than 3 years)
In cases of clinical progression following treatment with BTK inhibitors and BCL2 inhibitors (so-called “double-refractory” or “double-exposed” CLL), therapy with the non-covalently binding BTK inhibitor pirtobrutinib may be appropriate. The BRUIN-321 study, which randomly compared the use of pirtobrutinib versus idelalisib/rituximab or bendamustine/rituximab, was pivotal for approval. Based on n=238 patients, pirtobrutinib demonstrated a significantly better median PFS (14 months versus 8.7 months with SOC). The time to next treatment (TTNT) was also highly significantly longer with pirtobrutinib (24 months vs. 10.9 months with SOC) [43].
Resistance mutations in BTK and PLCG2 can arise during continuous therapy with covalent BTK inhibitors. The common C481S mutation confers resistance to ibrutinib, acalabrutinib, and zanubrutinib, while pirtobrutinib remains effective. In contrast, mutations at T474 and L528 also lead to resistance to pirtobrutinib. In the BRUIN-321 study, patients with PLCG2 mutations also showed a reduced response. Therefore, testing for resistance mutations is recommended before initiating pirtobrutinib in cases of disease progression following continuous prior therapy with a covalent BTKi. Such testing is not necessary, however, following a limited-duration combination therapy, as resistance mutations are extremely rare in relapse [48].
BTKi Withdrawal Flare
Abrupt discontinuation of a BTKi can lead to a so-called “withdrawal flare” within a few days to about two weeks: a rapid increase in lymphocytosis, enlargement of lymph nodes and the spleen, and occasionally new-onset B-symptoms. The cause is thought to be an excessive reactivation of B-cell receptor signaling following the cessation of BTK blockade. Clinically, this phenomenon cannot be reliably distinguished from true disease progression and, in particular, from a Richter transformation; therefore, in the event of rapid clinical deterioration following discontinuation of BTKi, a careful reevaluation (including imaging and biopsy, if necessary) should be performed.
A flare reaction is of particular practical relevance when switching drug classes (e.g., switching from a covalent BTKi to venetoclax-based therapy) as well as during unplanned treatment interruptions (e.g., perioperatively, due to toxicity, or infection). To prevent this, a transition that is as seamless as possible or a brief overlap is recommended when a change in agent is planned; if a treatment interruption is unavoidable, BTKi therapy should be resumed as soon as clinically feasible. In the event of a manifest BTKi withdrawal flare, either the BTK inhibitor should be restarted until the target dose for the next line of therapy is reached (e.g., 400 mg/day of venetoclax), or, alternatively, in cases of clinically pronounced symptoms, the early administration of a CD20 antibody (e.g., rituximab even before completion of the venetoclax ramp-up in the VenR regimen) should be considered.
6.1.2.2Transformation
In patients with transformation of CLL into large B-cell lymphoma (LBCL) in the sense of a Richter transformation, chemoimmunotherapy based on R-CHOP may be administered. However, the outcomes are very poor, with survival times of less than 1 year. For biologically young patients, a consolidating allogeneic stem cell transplant is therefore recommended whenever possible, particularly if the LBCL and CLL are clonally related (i.e., not an independent secondary lymphoma). If the patient is not a candidate for an allogeneic transplant, an autologous stem cell transplant may be considered instead [49]. If there are contraindications to an allogeneic or autologous stem cell transplant, immunotherapy using checkpoint inhibitors (off-label) may also be considered as a salvage option [50]. Recently, high efficacy (ORR 58.3%; 1-year OS 74.7%) for the combination of tislelizumab and zanubrutinib (RT1 study) in patients with Richter transformation [51]. A triple combination of venetoclax, obinutuzumab, and atezolizumab also proved highly effective, with an ORR of 67.9%, in the multicenter MOLTO study [52]. Whenever possible, patients should be treated as part of clinical trials.
For patients with transformation to Hodgkin lymphoma, treatment should be administered as for primary Hodgkin lymphoma.
Allogeneic stem cell transplantation is an option for high-risk patients; see Chapter 6.1.3 and Figure 3.
6.1.2.3Patients Refractory to BTKi and BCL2i
So-called “double-refractory” patients pose a particular therapeutic challenge; that is, those who have experienced disease progression both during ongoing cBTKi therapy and during or shortly after therapy containing venetoclax (or a combination of these drug classes) [53]. These patients have an extremely poor prognosis, with a median overall survival of approximately 2 years [54, 55]. Approved treatment options in this setting include the ncBTKi pirtobrutinib, the relatively poorly tolerated R-idelalisib, and—particularly when TP53 alterations are again found to be absent—chemoimmunotherapy. However, with documented PFS rates of <12 months (pirtobrutinib) or <9 months (R-idelalisib or R-bendamustine [43]), these regimens alone offer only very limited prospects; therefore, in suitable patients a consolidating allogeneic stem cell transplant (allo-SCT, see Chapter 6.1.3) should be discussed in the event of a response. CAR-T cells (Chapter 6.1.5) or—so far only in studies—BTK degraders are alternative options for consolidation or follow-up therapy.
6.1.3Allogeneic Stem Cell Transplantation
The availability of highly effective molecular therapies, along with the resulting improvement in prognosis, has significantly diminished the importance of allogeneic stem cell transplantation (allo-SCT) in CLL. However, it remains an option in situations associated with a relatively poor prognosis even with modern treatment options. Its efficacy has been demonstrated even after prior exposure to signaling pathway inhibitors, including in double-refractory patients [56], although it remains unclear at this time whether the latter benefit as much as patients responsive to signaling pathway inhibitors [55]. Allogeneic stem cell transplantation (allo-SCT) is generally worth considering when patients with TP53 alterations or a highly complex karyotype have become refractory to covalent BTK inhibitors or venetoclax, or when, regardless of TP53 status, both classes of agents have failed in cases of “double-refractory CLL” [57].
The indication, timing, and execution of a transplant—including donor selection—should be clarified in close collaboration with a transplant center before initiating salvage therapy. An important prognostic factor for achieving long-term disease control is the presence of remission at the time of allogeneic transplantation. Whenever possible, the transplant should be performed within the context of clinical trials.
6.1.4Autologous Stem Cell Transplantation
High-dose therapy with autologous blood stem cell transplantation can no longer be recommended for the treatment of CLL.
6.1.5CAR-T cell therapy
Although CLL was the first condition in which CAR-T cells were successfully used in adults, efficacy data for CLL have not kept pace with those for established B-cell NHL indications, particularly with regard to complete response rates. Based on the CLL004 study, in which an overall response rate of 47% and a rate of durable complete remissions (CRs) of 18% were achieved in double-refractory patients [58], Lisocel has been approved by the FDA for this patient population. However, the Lisocel manufacturer did not pursue EMA approval. In contrast to the CLL004 study and also the ZUMA-8 study with Brexucel, which primarily included patients with large tumor masses [41], the Heidelberg HD-CAR-1 study followed the concept of consolidative CAR-T therapy. Although 5 out of 7 patients treated with an effective dose of the CD19 product Heidagen lecleucel achieved an MRD-negative CR, the majority did not achieve sustained disease control (median PFS 12 months, 2-year PFS 40%) [55, 59]. Based on these data, Heidagen lecleucel received marketing authorization from the Paul Ehrlich Institute under Section 4b of the German Medicines Act (AMG) (Hospital Exemption) and is thus available in Germany for the treatment of double-refractory patients even outside of clinical trials.
The clinical significance of CAR-T therapy cannot yet be conclusively assessed; however, with the currently available products, a curative effect is likely to be achievable—if at all—only in a small proportion of double-refractory patients, in contrast to allogeneic stem cell transplantation (allo-SZT). Nevertheless, it represents a comparatively effective and well-tolerated addition to the previously inadequate therapeutic arsenal for double-refractory patients. CAR T-cell therapy should be administered within the framework of clinical trials whenever possible,
In patients with Richter transformation, retrospective, multicenter analyses have shown evidence of efficacy for the CAR T-cell products Axi-cel, Tisa-cel, and Liso-cel, which are approved for LBCL. However, with 2-year PFS rates of around 30%, the results appear to be somewhat poorer than those for de novo LBCL [60, 61]. Nevertheless, commercial CAR-T therapy may be considered as a potentially curative option in individual cases of relapse even outside of clinical trials, particularly if a response to salvage therapy can be achieved and allogeneic stem cell transplantation is not an option. The same applies to BiTEs (including epcoritamab) in refractory situations.
6.1.6Bispecific Antibodies and BTK Degraders
New data on bispecific antibodies (particularly epcoritamab) suggest high efficacy even in multi- (double/triple)-refractory patients. Preliminary analyses report high response rates with low CRS and ICANS frequencies, both as monotherapy (EPCORE-CLL1) [62] and in combination with venetoclax (AETHER Trial) [63].
In addition to CARs and BiTEs, so-called BTK degraders—a new class of drugs for CLL—are currently being tested in clinical trials and are showing, in some cases, high response rates exceeding 90% in refractory CLL study populations [64].
6.1.7Supportive Care and Management of Complications
CLL patients frequently experience infectious complications over the course of the disease, which are exacerbated by the decline in immunoglobulin concentrations and other mechanisms of acquired immunodeficiency; see Onkopedia’s entry on secondary immunodeficiencies (in German only). Particularly careful monitoring with intensive general internal medicine treatment—e.g., for chronic or recurrent bronchitis—is indicated. Prophylactic immunoglobulin replacement therapy reduces the risk of severe infections but has no significant effect on mortality. In June 2018, the EMA updated its guideline in the form of a Summary of Product Characteristics and established the following criteria for immunoglobulin replacement therapy in patients with secondary immunodeficiency [65]:
Severe or recurrent infections
Ineffective antimicrobial therapy
And evidence of a lack of specific antibody production (following vaccination) or serum IgG levels <4 g/L.
Age-appropriate vaccinations are recommended (see Onkopedia – Vaccinations (in German only)), although the production of specific antibodies may be reduced, and vaccinations should be administered whenever possible before initiating therapy. Travel vaccinations should only be administered after consultation with the treating specialist, as live vaccines, among other things, could pose a risk to the patient.
6.1.8Treatment of Autoimmune Phenomena
Autoimmune hemolytic anemia (AIHA) and immune thrombocytopenia (ITP) are common concomitant conditions in CLL [66]. AIHA is typically Coombs-positive. Cold agglutinins with detectable IgM antibodies are the exception. Coombs-negative hemolytic anemias have been described following prior therapy with purine analogs. Patients should be made aware of the particularly high risk of crises in the context of infections. Pure red cell aplasia (PRCA) is rarely observed. If AIHA or ITP occurs in isolation without other symptoms of CLL requiring treatment (see above), therapy with corticosteroids is indicated. Otherwise, treatment according to the algorithms mentioned above (see Tables 1 and 2), with a preference for anti-CD20-containing therapies (VenObi, Acalabrutinib-Obi, Venetoclax/Rituximab), is recommended, although there is also limited data on the use of targeted agents in patients with autoimmune phenomena [67].
6.2Systemic tumor therapy - Agents
The results of randomized clinical trials with the individual agents and combinations are summarized in Chronic Lymphocytic Leukemia: Study Results (in German only). Information on the approval status of drugs suitable for the treatment of CLL is listed in “Chronic Lymphocytic Leukemia: Approval Status for Germany, Austria, and Switzerland (in German only).”
6.2.1Acalabrutinib
Acalabrutinib is a Bruton’s tyrosine kinase (BTK) inhibitor. This kinase plays a central role in the development, differentiation, signal transduction, and survival of B lymphocytes. In the pivotal trial, acalabrutinib—either alone or in combination with obinutuzumab—significantly prolonged progression-free survival compared with chlorambucil/obinutuzumab in patients >65 years of age and in patients <65 years of age with comorbidities who had untreated CLL (acalabrutinib HR 0.2; acalabrutinib/obinutuzumab HR 0.1) [23]. Acalabrutinib in combination with obinutuzumab also led to an improvement in overall survival compared with chlorambucil/obinutuzumab (HR 0.55, p=0.0474) [68]. Patients with a confirmed del(17p13) or TP53 mutation benefit from acalabrutinib to nearly the same extent as patients without this risk factor; however, the addition of obinutuzumab does not improve outcomes compared with monotherapy.
Severe adverse events (CTCAE Grade 3/4) associated with acalabrutinib monotherapy in the ELEVATE-TN trial [23] included neutropenia (10%), anemia (7%), thrombocytopenia (3%), and pneumonia (2%). Diarrhea of all severities occurred in 35% of patients. Arrhythmias may occur with acalabrutinib, most commonly atrial fibrillation in 3–4% of patients. Diarrhea that occurs early in treatment is often self-limiting. Treatment with acalabrutinib may initially lead to lymphocytosis due to the flushing out of leukemia cells from lymphatic compartments. Other clinically relevant side effects include mild bleeding (43%), particularly from bruises (24%), and the development or worsening of hypertension, with 3% of cases classified as CTCAE Grade 3. Acalabrutinib is administered orally.
6.2.2Ibrutinib
Ibrutinib is a Bruton’s tyrosine kinase (BTK) inhibitor. This kinase plays a central role in the development, differentiation, signal transduction, and survival of B lymphocytes. In the pivotal trial, ibrutinib resulted in a significant prolongation of progression-free survival (hazard ratio 0.22) and overall survival (hazard ratio 0.43) in patients with relapsed or refractory CLL [69]. Patients with a confirmed del(17p13) or TP53 mutation benefit to nearly the same extent as patients without this risk factor. In untreated patients aged ≥65 years, ibrutinib is superior to chlorambucil monotherapy. Furthermore, ibrutinib-based therapy demonstrated superiority over both bendamustine/rituximab [22] and a combination of chlorambucil/obinutuzumab [70] in first-line therapy for older or less fit patients. Ibrutinib monotherapy was not inferior to the combination of ibrutinib and rituximab [22]. In the context of the E1912 study, the superiority of ibrutinib/rituximab over FCR in first-line therapy for young/fit CLL patients was also documented [21]; see Chronic Lymphocytic Leukemia – Study Results.
Severe adverse effects of ibrutinib monotherapy (CTCAE Grade 3/4) in the RESONATE studies [71] and the ALLIANCE study [22] included neutropenia (10–16%), anemia (4–12%), thrombocytopenia (2–7%), pneumonia (4–7%), and diarrhea (4%). Arrhythmias may occur with ibrutinib; the most common is atrial fibrillation, occurring in 5–8% of patients. Patients with severe arrhythmias (ventricular tachycardia, high-degree block) were excluded from the studies. Isolated cases of sudden death and invasive aspergillosis have been reported. Diarrhea that occurs early in treatment is often self-limiting. Treatment with ibrutinib initially leads to lymphocytosis due to the flushing out of leukemia cells from lymphatic compartments. Other clinically relevant side effects include skin hemorrhages (approximately 40%) and the development or worsening of arterial hypertension. The rate of worsening hypertension is reported to be 78% when a threshold of 130/90 mmHg is used, in accordance with the criteria of the American College of Cardiology. Based on the threshold of the European Society of Cardiology (ESC), this rate is calculated at 44% [72]. Ibrutinib is administered orally.
6.2.3Idelalisib
Idelalisib is a selective inhibitor of the delta isoform of phosphatidylinositol 3-kinase (PI3Kδ). This kinase plays an important role in B-cell receptor-induced signal transduction in mature B lymphocytes and in the pathogenesis of CLL. When combined with an anti-CD20 antibody (ofatumumab or rituximab), idelalisib leads to an increase in remission rates to 70–85%, a significant prolongation of progression-free survival (hazard ratio 0.2), and overall survival (hazard ratio 0.34–0.75) [73, 74]. Severe adverse effects of the combination therapy of idelalisib + rituximab (CTCAE Grade 3/4) included neutropenia (34%), thrombocytopenia (10%), anemia (5%), elevated transaminases (5%), diarrhea (4%), fever (3%), fatigue (3%), and chills (2%). In the spring of 2016, interim results from three ongoing studies on first-line therapy showed an increased number of infection-related deaths in the treatment arm receiving idelalisib. The report by the Pharmacovigilance Risk Assessment Committee (PRAC) of the European Medicines Agency (EMA) recommends antibiotic prophylaxis for Pneumocystis jirovecii and regular monitoring for signs of infection, particularly signs of CMV infection. Idelalisib is administered orally. The company will discontinue the distribution of idelalisib as of March 1, 2027, meaning that this medication will no longer be available for the treatment of CLL in the future.
6.2.4Liso-cel
On March 15, 2024, Liso-cel was approved by the FDA in the United States for patients with BTKi- and BCL2-i-refractory CLL, based on the CLL004 study [58]. However, approval in Germany is still pending. Based on 49 patients who received a higher dose of CAR-T cells (100 × 10⁶, dose level 2), the CLL004 study ( ) showed that 18% of patients achieved complete remission. Based on 117 patients, severe cytokine release syndrome (CRS) was observed in 9% of patients, and severe neurological events in 19%. A fatal case of macrophage activation syndrome was reported in one patient in this study.
6.2.5Obinutuzumab
Obinutuzumab is an anti-CD20 antibody with altered glycosylation. In treatment-naive patients with comorbidities, it led to a significant prolongation of progression-free survival (hazard ratio 0.39; median 11.5 months) when used in combination with chlorambucil compared to chlorambucil-rituximab therapy [75] and, in a later analysis, also in terms of overall survival (hazard ratio 0.76; median not reached) [76]. Severe adverse effects of combination therapy with chlorambucil (CTCAE Grade 3/4) included infusion-related reactions (21%), neutropenia (35%), thrombocytopenia (11%), and anemia (5%). Obinutuzumab is administered intravenously.
6.2.6Pirtobrutinib
Pirtobrutinib is a selective, non-covalently binding BTK inhibitor that was evaluated in a Phase I/II trial in patients with relapsed/refractory CLL/SLL (BRUIN). Among patients, the majority of whom (78%) had received a BTKi and some of whom had also received venetoclax (40.5%) as prior therapy, a response rate of 73.3% was observed with a median PFS of 19.6 months [77]. The most common adverse effects reported were infections (71%), bleeding (42.6%), and neutropenia (32.5%). In addition, the following adverse events occurred in this study with pirtobrutinib: hypertension (14.2%), atrial fibrillation/flutter (3.8%), and severe hemorrhages (2.2%). The so-called BRUIN-321 study, which randomly compared the use of pirtobrutinib against idelalisib/rituximab or bendamustine/rituximab, was relevant for regulatory approval. Based on 238 patients, a significantly better median PFS was observed with pirtobrutinib (14 months) compared to the standard-of-care arm (8.7 months). The time to next treatment (TTNT) was also significantly improved with pirtobrutinib, at 24 months (24 months vs. 10.9 months) [43]. The drug was approved by the FDA on December 1, 2023, for patients with double-refractory (BTKi, BCL2i) CLL. On March 31, 2025, the EMA granted approval, with pirtobrutinib already approved for patients who had previously been treated with a covalent BTK inhibitor alone; thus, patients do not necessarily have to be double-refractory. Pirtobrutinib was also recently tested as a first-line therapy in two randomized Phase III trials: In the BRUIN-313 trial, pirtobrutinib demonstrated a significant prolongation of progression-free survival (PFS) and a substantial reduction in risk compared with the standard therapy of bendamustine/rituximab [28]. The BRUIN-314 study further demonstrated the non-inferiority of pirtobrutinib compared to ibrutinib in terms of overall response rate, while also exhibiting a more favorable safety profile and fewer cardiac side effects [29]. On June 26, 2026, the Committee for Medicinal Products for Human Use (CHMP) of the European Medicines Agency (EMA) issued a positive recommendation to expand the marketing authorization for pirtobrutinib to include first-line treatment of CLL, based on these two studies.
6.2.7Rituximab
Rituximab is a chimeric anti-CD20 antibody. It was first approved for the treatment of patients with indolent lymphomas. Rituximab is effective as monotherapy for CLL; the effect is dose-dependent. In combination with fludarabine and cyclophosphamide (FCR), rituximab was the first agent to result in a significant prolongation of overall survival. The most common side effects of rituximab are immediately infusion-related and include fever, chills, nausea, and general malaise. Cytokine release syndrome can lead to severe hypotension with high fever, hypoxia, and the need for intensive care. The occurrence of cytokine release syndrome correlates with tumor burden and depends on the rituximab dosage. Side effects of FCR combination therapy classified as CTCAE Grade 3/4 include cytokine release syndrome, neutropenia (34%), infections (25%), thrombocytopenia (7%), and anemia (4%). Rituximab can be administered intravenously or subcutaneously. Currently, only intravenous administration is approved for CLL.
6.2.8Venetoclax
Venetoclax blocks the anti-apoptotic B-cell lymphoma-2 protein (BCL2), thereby inducing programmed cell death. In one of the two non-randomized registration studies, venetoclax resulted in partial or complete remission in 75% of pretreated patients with a del17p or TP53 mutation. Among patients without a del17p or TP53 mutation but who had previously been treated with a BCR signaling pathway inhibitor (ibrutinib or idelalisib), 67% achieved partial or complete remission. Furthermore, venetoclax demonstrates clinical activity in patients who have received prior treatment with chemoimmunotherapy and a BCR inhibitor, regardless of TP53 aberration status [44, 46]. Furthermore, data from a randomized trial comparing venetoclax to bendamustine were published as part of the MURANO study; response rates—including the MRD-negativity rate—and progression-free survival were significantly improved in favor of the venetoclax/rituximab combination (time-limited therapy over a total of 2 years), regardless of TP53 status [46]. Venetoclax is approved as monotherapy for first-line treatment of patients with 17p or TP53 mutations, provided the patient is not eligible for ibrutinib therapy. The combination of venetoclax and obinutuzumab (limited to a total treatment duration of approximately 10.5 months, corresponding to 12 cycles of venetoclax) was approved by the FDA and EMA in 2020 based on data from the CLL14 study [31]; for national regulations.
The most common side effects of venetoclax are neutropenia, diarrhea, nausea, anemia, upper respiratory tract infections, fatigue, and elevated blood phosphate levels. Severe side effects may include febrile neutropenia, pneumonia, and initial tumor lysis syndrome. To prevent tumor lysis syndrome, a dose escalation schedule for the first few weeks has been included in the prescribing information. It starts at 20 mg and reaches the target dose of 400 mg by week 5. Venetoclax is administered orally.
6.2.9Zanubrutinib
Zanubrutinib is a second-generation Bruton’s tyrosine kinase (BTK) inhibitor with more specific kinase inhibition compared to ibrutinib. In the SEQUOIA study, zanubrutinib monotherapy in patients >65 years of age or in patients <65 years of age with comorbidities and untreated CLL resulted in a significant prolongation of progression-free survival compared with bendamustine/rituximab (zanubrutinib HR 0.3), but not of overall survival. Patients with a confirmed del(17p13) or TP53 mutation benefit to nearly the same extent as patients without this risk factor; the same applies to those with an unmutated IGHV status.
Severe adverse events associated with zanubrutinib monotherapy (CTCAE Grade 3/4) in the SEQUOIA study [25] included, in particular, neutropenia (11%), anemia (0.4%), thrombocytopenia (2.1%), infections (16.3%), and pneumonia (1.7%). Diarrhea of all severities occurred in 13.8% of patients. Arrhythmias may occur with zanubrutinib; the most common was atrial fibrillation, observed in 1.7% of patients. Treatment with zanubrutinib may initially lead to lymphocytosis due to the flushing out of leukemia cells from lymphatic compartments. Other clinically relevant adverse effects include mild bleeding (28.3%), primarily from contusions (24.2%), and the development or worsening of arterial hypertension, with 6.3% of cases classified as CTCAE Grade 3. Zanubrutinib is administered orally.
7Rehabilitation
Patients should be informed early on about the options for outpatient and inpatient rehabilitation measures, as well as other entitlements arising from social welfare law. The patient’s preferences regarding the rehabilitation facility should be taken into account (in Germany, pursuant to Section 9 of SGB IX). Nevertheless, a recommendation for a facility specializing in oncology should be provided to ensure optimal rehabilitation outcomes.
8Follow-up
Follow-up care for asymptomatic patients should include a complete blood count every 3–6 months, along with a clinical examination of the lymph nodes, liver, and spleen. Radiological examinations using computed tomography (CT) or magnetic resonance imaging (MRI) are generally not necessary for the follow-up care of patients in remission. Attention should be paid to the occurrence of autoimmune cytopenias (autoimmune hemolytic anemia, immune thrombocytopenia) and infections. Furthermore, rapid lymph node enlargement, B-symptoms, and/or elevated LDH levels should prompt the exclusion not only of a CLL relapse but also of a transformation into a highly malignant lymphoma (Richter transformation). If a CLL relapse is clinically suspected, molecular (cytogenetic) testing should be repeated to definitively rule out newly emerged, treatment-relevant high-risk abnormalities (particularly del17p13 or TP53 mutation, complex karyotype).
Information on COVID-19 can be found in the Onkopedia COVID-19 guideline (in German only). The SARS-CoV-2 pandemic has not resulted in any changes regarding therapy or follow-up and monitoring examinations.
9References
Alaggio, Amador, Anagnostopoulos, et al., The 5th edition of the World Health Organization Classification of Hematolymphoid Tumors: Lymphoid Neoplasms. Leukemia, 2022. 36(7): pp. 1720–1748. DOI:10.1038/s41375-022-01620-2
Cancer Stat Facts: Leukemia—Chronic Lymphocytic Leukemia (CLL). 2021; Available from: https://seer.cancer.gov/statfacts/html/clyl.html
Sant, Allemani, Tereanu, et al., Incidence of hematologic malignancies in Europe by morphologic subtype: results of the HAEMACARE project. Blood, 2010. 116(19): pp. 3724–34. DOI:10.1182/blood-2010-05-282632
Bassig, Au, Mang, et al., Subtype-specific incidence rates of lymphoid malignancies in Hong Kong compared to the United States, 2001–2010. Cancer Epidemiol, 2016. 42: pp. 15–23. DOI:10.1016/j.canep.2016.02.007
Dohner, Stilgenbauer, Benner, et al., Genomic aberrations and survival in chronic lymphocytic leukemia. N Engl J Med, 2000. 343(26): pp. 1910–6. DOI:10.1056/NEJM200012283432602
Knisbacher, Lin, Hahn, et al., “Molecular map of chronic lymphocytic leukemia and its impact on outcome.” Nat Genet, 2022. 54(11): pp. 1664–1674. DOI:10.1038/s41588-022-01140-w
Burger, Gribben, The microenvironment in chronic lymphocytic leukemia (CLL) and other B-cell malignancies: insight into disease biology and new targeted therapies. Semin Cancer Biol, 2014. 24: pp. 71–81. DOI:10.1016/j.semcancer.2013.08.011
Occupational Diseases Regulation (BKV), Consumer Protection, Editor. 1997.
Goldin, Landgren, Marti, et al., “Familial Aspects of Chronic Lymphocytic Leukemia, Monoclonal B-Cell Lymphocytosis (MBL), and Related Lymphomas.” European J Clin Med Oncol, 2010. 2(1): pp. 119–126. PMID:21191471
Cerhan, Slager, “Familial predisposition and genetic risk factors for lymphoma.” *Blood*, 2015. 126(20): pp. 2265–73. DOI:10.1182/blood-2015-04-537498
Rawstron, Bennett, O’Connor, et al., “Monoclonal B-cell lymphocytosis and chronic lymphocytic leukemia.” N Engl J Med, 2008. 359(6): pp. 575–83. DOI:10.1056/NEJMoa075290
Strati, Shanafelt, Monoclonal B-cell lymphocytosis and early-stage chronic lymphocytic leukemia: diagnosis, natural history, and risk stratification. Blood, 2015. 126(4): pp. 454–62. DOI:10.1182/blood-2015-02-585059
Bohn et al.: Long-term event-free survival in patients with IGHV-mutated high-count monoclonal B-cell lymphocytosis and atypical, non-CLL-like phenotypes. ASH 2025;146:Suppl1, 2112, 2025.
Langerbeins, Robrecht, Nieper, et al., Ibrutinib in Early-Stage Chronic Lymphocytic Leukemia: The Randomized, Placebo-Controlled, Double-Blind, Phase III CLL12 Trial. J Clin Oncol, 2025. 43(4): pp. 392–402. DOI:10.1200/JCO.24.00975
Hallek, Cheson, Catovsky, et al., iwCLL guidelines for diagnosis, indications for treatment, response assessment, and supportive management of CLL. Blood, 2018. 131(25): pp. 2745–2760. DOI:10.1182/blood-2017-09-806398
Binet, Auquier, Dighiero, et al., A new prognostic classification of chronic lymphocytic leukemia derived from a multivariate survival analysis. Cancer, 1981. 48(1): pp. 198–206. DOI:10.1002/1097-0142(19810701)48:1<198::aid-cncr2820480131>3.0.co;2-v
Rai, Sawitsky, Cronkite, et al., Clinical staging of chronic lymphocytic leukemia. Blood, 1975. 46(2): pp. 219–34. PMID:1139039
International, An international prognostic index for patients with chronic lymphocytic leukemia (CLL-IPI): a meta-analysis of individual patient data. Lancet Oncol, 2016. 17(6): pp. 779–790. DOI:10.1016/S1470-2045(16)30029-8
Burger, Barr, Robak, et al., Final analysis of the RESONATE-2 study: up to 10 years of follow-up of first-line ibrutinib treatment for CLL/SLL. Blood, 2025. 146(18): pp. 2168–2176. DOI:10.1182/blood.2024028205
Tausch, Schneider, Stilgenbauer, Risk stratification in first-line CLL therapy: standard of care. Hematology Am Soc Hematol Educ Program, 2024. 2024(1): pp. 457–466. DOI:10.1182/hematology.2024000656
Woyach, Perez Burbano, Ruppert, et al., Follow-up from the A041202 study shows continued efficacy of ibrutinib regimens for older adults with CLL. Blood, 2024. 143(16): pp. 1616–1627. DOI:10.1182/blood.2023021959
Woyach, Ruppert, Heerema, et al., Ibrutinib Regimens versus Chemoimmunotherapy in Older Patients with Untreated CLL. N Engl J Med, 2018. 379(26): pp. 2517–2528. DOI:10.1056/NEJMoa1812836
Sharman, Egyed, Jurczak, et al., Efficacy and safety in a 4-year follow-up of the ELEVATE-TN study comparing acalabrutinib with or without obinutuzumab versus obinutuzumab plus chlorambucil in treatment-naive chronic lymphocytic leukemia. Leukemia, 2022. 36(4): pp. 1171–1175. DOI:10.1038/s41375-021-01485-x
Byrd, Hillmen, Ghia, et al., Acalabrutinib Versus Ibrutinib in Previously Treated Chronic Lymphocytic Leukemia: Results of the First Randomized Phase III Trial. J Clin Oncol, 2021. 39(31): pp. 3441–3452. DOI:10.1200/JCO.21.01210
Tam, Brown, Kahl, et al., Zanubrutinib versus bendamustine and rituximab in untreated chronic lymphocytic leukemia and small lymphocytic lymphoma (SEQUOIA): a randomized, controlled, phase 3 trial. Lancet Oncol, 2022. 23(8): pp. 1031–1043. DOI:10.1016/S1470-2045(22)00293-5
Hillmen, Eichhorst, Brown, et al., Zanubrutinib Versus Ibrutinib in Relapsed/Refractory Chronic Lymphocytic Leukemia and Small Lymphocytic Lymphoma: Interim Analysis of a Randomized Phase III Trial. J Clin Oncol, 2023. 41(5): pp. 1035–1045. DOI:10.1200/JCO.22.00510
Brown, Eichhorst, Hillmen, et al., Zanubrutinib or Ibrutinib in Relapsed or Refractory Chronic Lymphocytic Leukemia. N Engl J Med, 2023. 388(4): pp. 319–332. DOI:10.1056/NEJMoa2211582
Jurczak, Kwiatek, Czyz, et al., BRUIN CLL-313: Randomized Phase III Trial of Pirtobrutinib Versus Bendamustine Plus Rituximab in Untreated Patients With Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma. J Clin Oncol, 2026. 44(6): pp. 466–475. DOI:10.1200/JCO-25-02380
Woyach, Qiu, Grosicki, et al., Pirtobrutinib Versus Ibrutinib in Treatment-Naive and Relapsed/Refractory Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma. J Clin Oncol, 2026. 44(6): pp. 476–485. DOI:10.1200/JCO-25-02477
Fischer, Cramer, Busch, et al., “Bendamustine in combination with rituximab for previously untreated patients with chronic lymphocytic leukemia: a multicenter phase II trial of the German Chronic Lymphocytic Leukemia Study Group.” J Clin Oncol, 2012. 30(26): pp. 3209–16. DOI:10.1200/JCO.2011.39.2688
Al-Sawaf, Zhang, Lu, et al., Minimal Residual Disease Dynamics after Venetoclax-Obinutuzumab Treatment: Extended Off-Treatment Follow-up From the Randomized CLL14 Study. J Clin Oncol, 2021. 39(36): pp. 4049–4060. DOI:10.1200/JCO.21.01181
Al-Sawaf, Zhang, Jin, et al., Transcriptomic profiles and 5-year results from the randomized CLL14 study of venetoclax plus obinutuzumab versus chlorambucil plus obinutuzumab in chronic lymphocytic leukemia. Nat Commun, 2023. 14(1): p. 2147. DOI:10.1038/s41467-023-37648-w
Furstenau, Kater, Robrecht, et al., First-line venetoclax combinations versus chemoimmunotherapy in fit patients with chronic lymphocytic leukemia (GAIA/CLL13): 4-year follow-up from a multicenter, open-label, randomized, phase 3 trial. Lancet Oncol, 2024. 25(6): pp. 744–759. DOI:10.1016/S1470-2045(24)00196-7
Al-Sawaf, Stumpf, Zhang, et al., Fixed-Duration versus Continuous Treatment for Chronic Lymphocytic Leukemia. N Engl J Med, 2026. 394(11): pp. 1084–1096. DOI:10.1056/NEJMoa2515458
Kater, Owen, Moreno, et al., Fixed-Duration Ibrutinib-Venetoclax in Patients with Chronic Lymphocytic Leukemia and Comorbidities. NEJM Evid, 2022. 1(7): p. EVIDoa2200006. DOI:10.1056/EVIDoa2200006
Tam, Allan, Siddiqi, et al., Fixed-duration ibrutinib plus venetoclax for first-line treatment of CLL: primary analysis of the CAPTIVATE FD cohort. Blood, 2022. 139(22): pp. 3278–3289. DOI:10.1182/blood.2021014488
Jain, Croner, Allan, et al., Absence of BTK, BCL2, and PLCG2 Mutations in Chronic Lymphocytic Leukemia Relapsing after First-Line Treatment with Fixed-Duration Ibrutinib plus Venetoclax. Clin Cancer Res, 2024. 30(3): pp. 498–505. DOI:10.1158/1078-0432.CCR-22-3934
Brown, Seymour, Jurczak, et al., Fixed-Duration Acalabrutinib Combinations in Untreated Chronic Lymphocytic Leukemia. N Engl J Med, 2025. 392(8): pp. 748–762. DOI:10.1056/NEJMoa2409804
Simon, Ligtvoet, Bohn, et al., Acalabrutinib treatment for older (aged ≥80 years) and/or frail patients with CLL: primary endpoint analysis of the CLL-Frail trial. Blood, 2025. 146(26): pp. 3153–3162. DOI:10.1182/blood.2025028550
Sharman JP, Egyed M, Jurczak W et al.: 636 Acalabrutinib ± Obinutuzumab vs. Obinutuzumab + Chlorambucil in Treatment-Naive Chronic Lymphocytic Leukemia: 6-Year Follow-up of the Elevate-TN Trial. 2023. https://ash.confex.com/ash/2023/webprogram/Paper174750.html
Davids, Ryan, Lampson, et al., Phase II Study of Acalabrutinib, Venetoclax, and Obinutuzumab in a Treatment-Naive Chronic Lymphocytic Leukemia Population Enriched for High-Risk Disease. J Clin Oncol, 2025. 43(7): pp. 788–799. DOI:10.1200/JCO-24-02503
Ghia, Pluta, Wach, et al., ASCEND: Phase III, Randomized Trial of Acalabrutinib Versus Idelalisib Plus Rituximab or Bendamustine Plus Rituximab in Relapsed or Refractory Chronic Lymphocytic Leukemia. J Clin Oncol, 2020. 38(25): pp. 2849–2861. DOI:10.1200/JCO.19.03355
Sharman, Munir, Grosicki, et al., Phase III Trial of Pirtobrutinib Versus Idelalisib/Rituximab or Bendamustine/Rituximab in Covalent Bruton Tyrosine Kinase Inhibitor-Pretreated Chronic Lymphocytic Leukemia/Small Lymphocytic Lymphoma (BRUIN CLL-321). J Clin Oncol, 2025. 43(22): pp. 2538–2549. DOI:10.1200/JCO-25-00166
Seymour, Kipps, Eichhorst, et al., Venetoclax-Rituximab in Relapsed or Refractory Chronic Lymphocytic Leukemia. N Engl J Med, 2018. 378(12): pp. 1107–1120. DOI:10.1056/NEJMoa1713976
Seymour, Kipps, Eichhorst, et al., Enduring undetectable MRD and updated outcomes in relapsed/refractory CLL after fixed-duration venetoclax-rituximab. Blood, 2022. 140(8): pp. 839–850. DOI:10.1182/blood.2021015014
Stilgenbauer, Eichhorst, Schetelig, et al., Venetoclax in relapsed or refractory chronic lymphocytic leukemia with 17p deletion: a multicenter, open-label, phase 2 study. Lancet Oncol, 2016. 17(6): pp. 768–778. DOI:10.1016/S1470-2045(16)30019-5
Stilgenbauer, Eichhorst, Schetelig, et al., “Venetoclax for Patients With Chronic Lymphocytic Leukemia With 17p Deletion: Results From the Full Population of a Phase II Pivotal Trial.” J Clin Oncol, 2018. 36(19): pp. 1973–1980. DOI:10.1200/JCO.2017.76.6840
Naeem, Utro, Wang, et al., Pirtobrutinib targets BTK C481S in ibrutinib-resistant CLL, but second-site BTK mutations lead to resistance. Blood Adv, 2023. 7(9): pp. 1929–1943. DOI:10.1182/bloodadvances.2022008447
S3 Guideline on Diagnosis, Treatment, and Follow-up Care for Patients with Chronic Lymphocytic Leukemia (CLL). 2018, Oncology Guidelines Program of the Association of Scientific Medical Societies (AWMF), the German Cancer Society (DKG), and the German Cancer Aid Foundation (DKH). https://www.awmf.org/leitlinien/detail/ll/018-032OL.html
Ding W; Dong H; Call TG et al.: PD-1 Blockade with Pembrolizumab (MK-3475) in Relapsed/Refractory CLL Including Richter Transformation: An Early Efficacy Report from a Phase 2 Trial (MC1485). 2016. https://ash.confex.com/ash/2015/webprogram/Paper84816.html
Al-Sawaf, Ligtvoet, Robrecht, et al., Tislelizumab plus zanubrutinib for Richter transformation: the Phase 2 RT1 trial. Nat Med, 2024. 30(1): pp. 240–248. DOI:10.1038/s41591-023-02722-9
Tedeschi, Frustaci, Condoluci, et al., Atezolizumab, venetoclax, and obinutuzumab combination in Richter transformation diffuse large B-cell lymphoma (MOLTO): a multicenter, single-arm, phase 2 trial. Lancet Oncol, 2024. 25(10): pp. 1298–1309. DOI:10.1016/s1470-2045(24)00396-6
Grainger, Thompson, Cheah, Doubling down: the new approach to the clinical management of double-refractory chronic lymphocytic leukemia. Blood, 2025. 146(2): pp. 145–154. DOI:10.1182/blood.2024024893
Yoon, Zhou, Mikhaleva, et al., Characteristics and Outcomes of Patients with Double-Refractory and Double-Exposed Chronic Lymphocytic Leukemia. Blood Adv, 2025. 9(11): pp. 2808–2817. DOI:10.1182/bloodadvances.2025016006
Kauer, Krämer, Derigs, et al., High-risk single-refractory and double-refractory chronic lymphocytic leukemia: feasibility and impact of alloHCT. Blood Advances, 2026. 10(16): pp. 5698–5705. DOI:10.1182/bloodadvances.2026020219
Roeker, Dreger, Brown, et al., Allogeneic stem cell transplantation for chronic lymphocytic leukemia in the era of novel agents. Blood Adv, 2020. 4(16): pp. 3977–3989. DOI:10.1182/bloodadvances.2020001956
Dreger, “Is There a Role for Cellular Therapy in Chronic Lymphocytic Leukemia?” Cancer J, 2021. 27(4): pp. 297–305. DOI:10.1097/PPO.0000000000000532
Siddiqi, Maloney, Kenderian, et al., Lisocabtagene maraleucel in chronic lymphocytic leukemia and small lymphocytic lymphoma (TRANSCEND CLL 004): a multicenter, open-label, single-arm, phase 1-2 study. Lancet, 2023. 402(10402): pp. 641–654. DOI:10.1016/S0140-6736(23)01052-8
Derigs, Schubert, Dreger, et al., Third-generation anti-CD19 CAR T cells for relapsed/refractory chronic lymphocytic leukemia: a phase 1/2 study. Leukemia, 2024. 38(11): pp. 2419–2428. DOI:10.1038/s41375-024-02392-7
Kittai, Bond, Huang, et al., Anti-CD19 Chimeric Antigen Receptor T-Cell Therapy for Richter Transformation: An International, Multicenter, Retrospective Study. J Clin Oncol, 2024. 42(17): pp. 2071–2079. DOI:10.1200/JCO.24.00033
Nadiminti, Ahn, Patel, et al., Chimeric Antigen Receptor T-Cell Therapy for Richter Transformation: A CIBMTR Analysis. Transplant Cell Ther, 2025. 31(12): p. 1000 e1-1000 e11. DOI:10.1016/j.jtct.2025.07.021
Danilov, Fakhri, Awan, et al., Epcoritamab Monotherapy in Patients (Pts) with Relapsed or Refractory (R/R) Chronic Lymphocytic Leukemia (CLL): Results from the CLL Expansion and Optimization Cohorts of Epcore CLL-1. Blood, 2024. 144(Supplement 1): p. 883-883. DOI:10.1182/blood-2024-199708
Kater AP, Levin MD, Dubois J, et al.: Fixed-duration venetoclax plus epcoritamab demonstrates favorable tolerability and high response rates with early molecular responses in r/r CLL/SLL: interim analysis of the randomized HOVON 165/Aether trial. EHA Library, 2026. EHA-3784 Short: S153. https://library.ehaweb.org/eha/2026/eha-2026/4206707/
Sharma, Jiang, Liu, Novel BTK inhibitors and degraders for relapsed/refractory CLL/SLL: latest updates from the ASH 2025 annual meeting. J Hematol Oncol, 2026. 19(1). DOI:10.1186/s13045-026-01810-w
European Medicines Agency (EMA): Guideline on the core Summary of Product Characteristics (SmPC) for human normal immunoglobulin for intravenous administration (IVIG). 2021. https://www.ema.europa.eu/en/documents/scientific-guideline/guideline-core-smpc-human-normal-immunoglobulin-intravenous-administration-ivig-rev-6_en
Hodgson, Ferrer, Pereira, et al., Autoimmune cytopenia in chronic lymphocytic leukemia: diagnosis and treatment. Br J Haematol, 2011. 154(1): pp. 14–22. DOI:10.1111/j.1365-2141.2011.08707.x
Vitale, Salvetti, Griggio, et al., Preexisting and treatment-emergent autoimmune cytopenias in patients with CLL treated with targeted drugs. Blood, 2021. 137(25): pp. 3507–3517. DOI:10.1182/blood.2020008201
Sharman JP, Egyed M, Jurczak W et al.: Acalabrutinib ± Obinutuzumab vs. Obinutuzumab + Chlorambucil in Treatment-Naïve Chronic Lymphocytic Leukemia: 5-Year Follow-Up of Elevate-TN. 2022. P666, https://ash.confex.com/ash/2023/webprogram/Paper174750.html
Fischer, Al-Sawaf, Bahlo, et al., “Venetoclax and Obinutuzumab in Patients with CLL and Coexisting Conditions.” N Engl J Med, 2019. 380(23): pp. 2225–2236. DOI:10.1056/NEJMoa1815281
Moreno, Greil, Demirkan, et al., First-line treatment of chronic lymphocytic leukemia with ibrutinib plus obinutuzumab versus chlorambucil plus obinutuzumab: final analysis of the randomized, phase III iLLUMINATE trial. Haematologica, 2022. 107(9): pp. 2108–2120. DOI:10.3324/haematol.2021.279012
Byrd, Brown, O’Brien, et al., Ibrutinib versus ofatumumab in previously treated chronic lymphocytic leukemia. N Engl J Med, 2014. 371(3): pp. 213–23. DOI:10.1056/NEJMoa1400376
Dickerson, Wiczer, Waller, et al., “Hypertension and incident cardiovascular events following ibrutinib initiation.” *Blood*, 2019. 134(22): pp. 1919–1928. DOI:10.1182/blood.2019000840
Furman, Sharman, Coutre, et al., “Idelalisib and rituximab in relapsed chronic lymphocytic leukemia.” N Engl J Med, 2014. 370(11): pp. 997–1007. DOI:10.1056/NEJMoa1315226
Jones, Robak, Brown, et al., Efficacy and safety of idelalisib in combination with ofatumumab for previously treated chronic lymphocytic leukemia: an open-label, randomized phase 3 trial. Lancet Haematol, 2017. 4(3): pp. e114–e126. DOI:10.1016/S2352-3026(17)30019-4
Goede, Fischer, Busch, et al., Obinutuzumab plus chlorambucil in patients with CLL and coexisting conditions. N Engl J Med, 2014. 370(12): p. 1101-10. DOI:10.1056/NEJMoa1313984
Goede V; Fischer K; Dyer MJS; et al.: Overall survival benefit of obinutuzumab over rituximab when combined with chlorambucil in patients with chronic lymphocytic leukemia and comorbidities. Final survival analysis of the CLL11 study. 2018. https://learningcenter.ehaweb.org/eha/2018/stockholm/215923/valentin.goede.overall.survival.benefit.of.obinutuzumab.over.rituximab.when.html
Mato, Woyach, Brown, et al., Pirtobrutinib after a Covalent BTK Inhibitor in Chronic Lymphocytic Leukemia. N Engl J Med, 2023. 389(1): pp. 33–44. DOI:10.1056/NEJMoa2300696
10Ongoing Studies
11Systemic Therapy - Protocols
12Study Results
13Certification status
14Links
Malignant Lymphoma Competence Network
www.kompetenznetz-leukaemie.de
German Leukemia & Lymphoma Aid, Inc.
German CLL Study Group
16Disclosure of Potential Conflicts of Interest
according to the rules of the responsible Medical Societies.
Download
Reference:
Quellenangabe:
Onkopedia-Leitlinien werden kontinuierlich an den Stand des Wissens angepasst. Die jeweils gültige Version, AGB und Nutzungsbedingungen finden Sie unter www.onkopedia.com.
Für die kommerzielle Nutzung wenden Sie sich bitte an onkopedia@dgho.de.
Onkopedia guidelines are continuously adapted to the state of knowledge. The currently valid version, terms of use and general terms and conditions can be found at onkopedia-guidelines.info.
For commercial use, please contact onkopedia@dgho.de.
