

Pleural Mesothelioma
Compliance rules
1Summary
Pleural mesotheliomas are rare tumors of the pleura and account for approximately 1% of cancer deaths among men and 0.3% among women in Germany. The relative 5-year survival rate is markedly poor, at 9% for men and 24% for women. The median age at diagnosis is 74 years for women and 75 years for men. Approximately 1,600 people are newly diagnosed with pleural mesothelioma each year in Germany. The main risk factor is exposure to asbestos fibers, usually occupational, particularly to asbestos that is only weakly bound to building materials and has a high fiber content.
Clinically, the disease often does not manifest until it has reached an advanced stage, presenting with pleural effusions, chest pain and dyspnea, as well as a nonspecific reduction in physical performance and/or weight loss. Asbestosis-related pleural mesotheliomas may be recognized as occupational diseases by workers’ compensation insurers.
The therapy of pleural mesothelioma generally includes local and systemic treatment options. The individual approach is primarily guided by the histological subtype and the extent of lymph node involvement as well as patient age and comorbidities. As a local treatment, extended pleurectomy/decortication (eP/D) may be offered to carefully selected patients with epithelioid histology and very limited disease as part of a multimodal therapeutic approach at a center with high surgical expertise. eP/D, accompanied by neoadjuvant or adjuvant systemic therapy - in this case, combination chemotherapy with cisplatin and pemetrexed - aims to achieve the greatest possible disease control; however, local and locoregional relapses are common, as achieving a complete R0 resection is effectively impossible. In advanced, metastatic or recurrent settings, treatment involving immune checkpoint inhibitors (ICIs) should be administered regardless of the histological subtype; for the non-epithelioid subtype, ICI therapy is recommended as the primary treatment.
2Basics
2.1Definition and Basic Information
Pleural mesotheliomas are malignant tumors that originate from the serous membranes of the pleura. Histologically, three types are distinguished: epithelioid, biphasic, and sarcomatoid [1, 2]. Biphasic and sarcomatoid mesotheliomas are also grouped under the term “non-epithelioid subtypes.” The epithelioid type is the most common subtype, accounting for 50-60% of cases. Clinically, the most common site of metastasis is the (contralateral) pleura. Metastasis to the thoracic lymph nodes, the lung and the peritoneum is also common.
The statements and recommendations in this guideline refer to malignant pleural mesothelioma and not to mesotheliomas of the peritoneum (ICD-10: C45.1), the tunica vaginalis testis (C45.7, C63.7), the pericardium (C45.2) or benign mesotheliomas (pleura: D19.1, peritoneum: D19.2, other sites: D19.7).
2.2Epidemiology
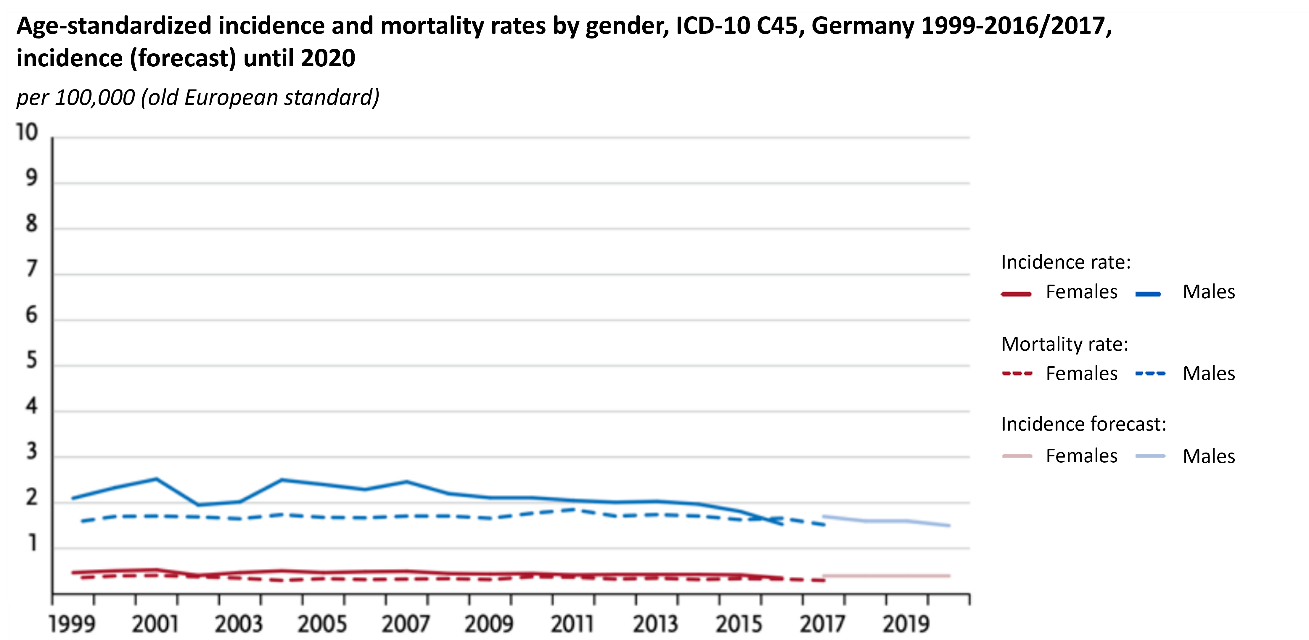
Malignant pleural mesothelioma (C45.0) is a rare malignant tumor caused primarily by the inhalation of asbestos fibers. Due to the long latency period between exposure, often occupational, and tumor diagnosis, new cases continue to occur even more than 40 years after the first legal restrictions have been imposed and nearly 30 years after the final ban on the use of asbestos. In 2023, 1,350 cases were recorded in the German cancer registries, with men accounting for the vast majority (1,060 cases) (table 1). The number of new cases has been declining slightly only since 2014 (1,425 cases) (figure 1 and figure 2). Incidence rates in age groups up to 70 years have recently fallen significantly among men, while they continue to rise among those over 80. Accordingly, the median age at diagnosis has risen from 72 to 74 years over the past 10 years [3, 4]. It should be noted here that the data from the Robert Koch Institute (RKI) presented in figures 1 and 2, as well as in table 1, refer to all types of mesotheliomas and thus include both pleural mesothelioma (the largest group) and, for example, peritoneal and pericardial mesothelioma [5]. Separate data for pleural mesothelioma alone are not available.
Incidence | 2021 | 2022 | 2023 | |||
Women | Men | Women | Men | Women | Men | |
New Cases | 320 | 1,230 | 300 | 1,160 | 290 | 1,060 |
Crude incidence rate1 | 0.7 | 3.0 | 0.7 | 2.8 | 0.7 | 2.6 |
Standardized incidence rate 1,2 | 0.4 | 1.6 | 0.3 | 1.5 | 0.3 | 1.3 |
Median age at onset3 | 76 | 78 | 76 | 78 | 74 | 79 |
Mortality | 2021 | 2022 | 2023 | |||
Women | Men | Women | Men | Women | Men | |
Deaths | 242 | 1,046 | 221 | 1,014 | 238 | 907 |
Crude death rate1 | 0.6 | 2.5 | 0.5 | 2.5 | 0.6 | 2.2 |
Standardized mortality rate 1,2 | 0.2 | 1.3 | 0.2 | 1.3 | 0.3 | 1.1 |
Median age at death3 | 79 | 79 | 79 | 80 | 77 | 80 |
Prevalence and Survival Rates | 5 years | 10 years | 25 years | |||
| Women | Men | Women | Men | Women | Men |
Prevalence | 600 | 1,700 | 900 | 2,300 | 1,500 | 3,500 |
Absolute survival rate (2021-2023)4 | 20 | 7 | 12 | 3 |
|
|
Relative survival rate (2021-2023)4 | 24 | 9 | 16 | 5 |
|
|
2 age-standardized according to the European population;
3 in years;
4 as a percentage
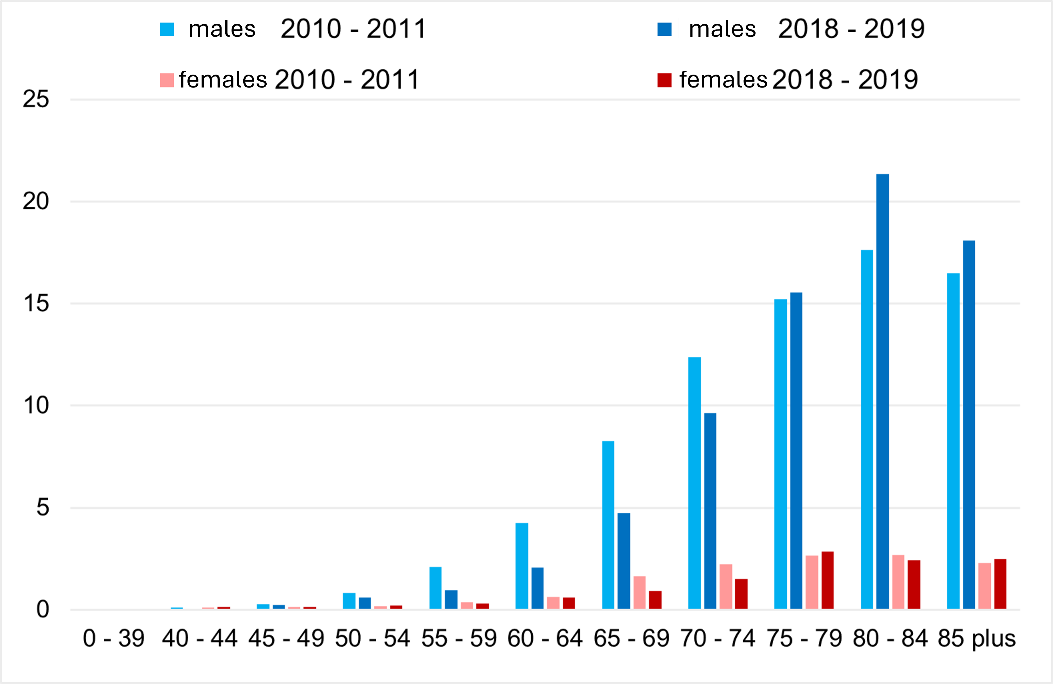
Relatively high incidence rates are observed in northwestern Germany in former shipbuilding sites, such as in the state of Bremen and neighboring regions, and to some extent also at steel industry sites, such as in the Ruhr region [3, 4, 5]. Based on figures from the RKI/ZfKRD, only approximately 71% of mesotheliomas diagnosed in Germany - the majority of which affect the pleura - are reported to workers’ compensation insurers as suspected cases of occupational disease [2, 3, 4, 5]. Histologically, a distinction is made between epithelioid (60-80%), sarcomatoid (< 10%), and biphasic (10-15%) forms [2]. In addition, there are rare variant forms [2].
The prognosis is poor: the 5-year survival rate is 10-34% for women and 9-17% for men [5]. The 10-year survival rate is 10-23% for women and 6-11% for men [5].
2.3Risk Factors
Mesotheliomas are primarily caused by fibrous minerals, with asbestos, in the form of imported blue (amphibole) or white (chrysotile) asbestos, being the most significant cause in Germany [4]. There are no natural asbestos deposits in Germany suitable for mining.
Other hazardous fibrous minerals, such as erionite and other zeolites, are found in Germany as associated minerals in basalt rocks, e.g., at Ettringer Bellerberg (Rheinland-Pfalz) or near Allendorf (Hessen) [6, 7]. No increased incidence of mesothelioma has been observed in the corresponding counties [8, 9].
Based on current knowledge, it is unlikely that man-made mineral fibers cause mesothelioma in humans [10]. Exposure to multi-walled carbon nanotubes (MWCNTs) can cause pleural mesothelioma in animal studies [11]. Since no epidemiological data are yet available due to the relatively short history of MWCNT use, lawmakers have enacted regulations to protect workers exposed to MWCNTs [12].
Previous radiation therapy to the thorax can lead to mesothelioma. In very rare cases, chronic inflammatory processes, BAP1 mutations, or an idiopathic cause may also trigger the disease [13]. Asbestos was used in significant quantities until a near-complete ban on its manufacturing and use was enacted in Germany in 1993 [14, 15]. The greatest risk today, and for the foreseeable future, is the improper handling of asbestos-containing materials still present in buildings. The geographic distribution of cases therefore shows a higher incidence in areas where large amounts of asbestos were processed in the past. A peak in the incidence of diseases was theoretically predicted due to the asbestos ban, but this could not be confirmed in reality as a long-term trend in Germany by 2020 [16, 17]. However, the number of new cases recorded annually by the RKI’s Center for Cancer Registry Data fell from 1,652 to 1,348 reports between 2019 and 2023. A certain degree of uncertainty arises, however, from the fact that, globally, the use of asbestos remains permitted in principle in some countries after 1993 [18, 19].
2.4Recognition as an Occupational Disease
Asbestos-related mesotheliomas of the pleura, the peritoneum (including the tunica vaginalis testis), and the pericardium may be recognized as occupational disease No. 4105 by workers’ compensation insurers [20].
In addition to malignant mesotheliomas of the pleura (C45.0), peritoneum (C45.1), tunica vaginalis testis (C45.7, C63.7), and pericardium (C45.2), well-differentiated papillary mesothelial tumors (WDPMT)/benign mesotheliomas (pleura: D19.0, peritoneum: D19.1, other locations: D19.7 according to the German ICD) among the clinical conditions covered by BK No. 4105.
Mesotheliomas are referred to as “signal tumors” for asbestos exposure [21]. When diagnosing mesothelioma, healthcare providers are legally required under Section 202 of the German SGB VII to submit a report of a suspected occupational disease for BK No. 4105, in accordance with the Occupational Diseases Ordinance, to the competent statutory workers’ compensation insurance provider or the local labor inspectorate if there is reasonable suspicion (Form available at: https://www.dguv.de/medien/formtexte/aerzte/f_6000/f6000). WDPMT [22] and mesothelioma in situ [21, 22, 23] are also considered mesotheliomas in this context.
For a report of a suspected occupational disease involving mesothelioma, neither smoking status nor the level or duration of asbestos exposure is decisive; the only determining factor is whether asbestos exposure occurred in the course of an activity covered by workers’ compensation insurance [24]. Even so-called “bystanders” or those with low levels of exposure may already have a fourfold increased risk of dying from mesothelioma compared to the general population [25].
In terms of medical history, it is sometimes not the obvious factors that are decisive (e.g., washing work clothes at home [an uninsured activity]), but rather details from long ago (e.g., handling asbestos insulation wool, using or working with asbestos-containing plaster, sanding down adhesives or sealants, or improper handling of Bunsen burner safety grids or equipment with asbestos heat shields).
Details regarding the medical evaluation as part of the occupational disease recognition process can be found in the Falkensteiner Recommendation [24]. Between 1994 and 2018, 19,017 men and 1,030 women died in Germany as a result of occupational disease No. 4105, more than from any other occupationally caused cancer [26, 27]. Mesothelioma, as an occupational disease, accounts for the largest single occupational disease-related expense item, 345.5 million Euros, of the total volume of benefits for occupational diseases paid by workers’ compensation insurers in 2024 [28].
You can find the latest information on the website of the German Mesothelioma Registry (http://www.mesotheliomregister.de/)
3Prevention and Early Detection
3.1Prevention and Screening
The most important action for preventing mesothelioma in Germany was the 1993 ban on the use of asbestos. Nevertheless, occupational exposure to legacy asbestos sites cannot always be avoided. In such cases, the consistent application of occupational safety measures is essential when working with legacy asbestos sites cannot be avoided.
The statutory workers’ compensation insurance providers issue preventive care recommendations before, during, and after the end of occupational asbestos exposure [28]. Even after the termination of activities in which health problems may arise following prolonged latency periods, follow-up preventive care must be offered in accordance with the German Regulation on Occupational Health Care (ArbMedVV). Therefore, insured individuals are entitled to receive occupational health care beyond the end of their working lives, even after the termination of an activity in which they were exposed to asbestos. Employers may, with the consent of the employees, transfer their obligation to provide follow-up preventive care to the competent workers’ compensation insurance provider after the employment relationship has ended. The central service agency of the workers’ compensation insurance providers for organizing follow-up preventive care related to asbestos is the German Health Prevention Service (GVS) [29].
3.2Early Detection
In addition to the diagnostic methods used in post-exposure preventive care, the German statutory accident insurance system offers insured persons the use of further diagnostic methods (e.g., the Expanded Preventive Care Program for the early detection of mesothelioma using blood-based biomarkers, EVA-Mesothel). The Institute for Prevention and Occupational Medicine of the German Statutory Accident Insurance - an institute of Ruhr University Bochum (IPA) - published the results of the MoMar study [24]. In a prospective longitudinal study, 2,769 participants with a recognized occupational disease code 4103 (asbestosis or pleural disease caused by asbestos dust) were examined annually, for a total of 12,548 examinations. The results showed that the risk of mesothelioma in this high-risk group was increased 17.6-fold compared to the general population [30]. The combination of the serum markers calretinin and mesothelin demonstrated a sensitivity of approximately 45% and a specificity of 98% for pleural and peritoneal mesotheliomas. Malignant pleural or peritoneal mesothelioma could be detected up to twelve months before clinical diagnosis. Based on these results, these biomarkers may provide a previous indication of mesothelioma that is more accurate than what can be achieved through the evaluation of clinically relevant symptoms. For this reason, workers’ compensation insurers offer EVA-Mesothel to individuals in the relevant high-risk groups. During a pilot phase from April 2023 to August 2025, 706 biomarker tests were conducted on individuals with a recognized occupational disease, resulting in the diagnosis of 4,103 (asbestosis/asbestos-related pleural changes) were identified, and three cases of mesothelioma were diagnosed among 31 suspected cases, two of which were non-epithelioid mesotheliomas at clinical stage T2. Since September 2025, EVA-Mesothel has been gradually rolled out nationwide [28].
Various studies on the treatment of mesotheliomas show an improved prognosis with early initiation of therapy [30, 31, 32, 33]. The oncological principle that previous diagnosis, and thus previous treatment, improves the prognosis is therefore also applicable to mesotheliomas [34, 35]. Early detection of mesothelioma is therefore of particular importance. Given that our understanding of the diagnosis, treatment, and prognosis of mesothelioma, particularly in the context of early detection using biomarkers, still needs to be improved, the use of biomarkers in clinical practice should be scientifically monitored. In the case of EVA-Mesothel, this scientific monitoring takes the form of the EVA-Mesothel-Monitor epidemiological study.
4Clinical Characteristics
Pleural mesotheliomas often present with symptoms such as dyspnea, a dry cough, and chest pain. In addition, nonspecific symptoms such as fatigue and unintentional weight loss may occur. A unilateral pleural effusion is often detected during sonographic and radiological examinations.
5Diagnosis
5.1Diagnostics
5.1.1Imaging and Biopsy
When new, particularly unilateral, pleural effusions occur, pleural mesothelioma should be considered as part of the differential diagnosis. Among a total of 2,263 patients with unilateral pleural effusions, mesothelioma was diagnosed in just under a quarter within one year [36, 37, 38, 39, 40, 41, 42, 43]. Based solely on medical history, clinical symptoms, and radiological imaging, the diagnosis of pleural mesothelioma cannot be confirmed or ruled out with sufficient certainty. Therefore, if pleural mesothelioma is suspected, histological evaluation should be pursued to establish a definitive diagnosis. Due to the relatively low incidence of pleural mesothelioma, diagnosis and treatment planning for this condition should be conducted at a center specializing in this disease. If pleural mesothelioma is suspected, in addition to the clinical history, an occupational history of both the patient and their spouse should be obtained to assess potential asbestos exposure.
In addition to the physical examination, at least a standard ultrasound of the pleura (while the patient is seated) or a chest X-ray should be performed initially to check for pleural effusion. However, particularly when determining the justification for a chest X-ray, it is important to note that follow-up examinations will generally be necessary. These include more sensitive procedures such as a contrast-enhanced chest computed tomography (CT) [44, 45] or a Fibroblast Activation Protein Inhibitor Positron Emission Tomographie-CT (FAPI-PET-CT) [46]. If a pleural effusion is present and pleural mesothelioma is suspected, it should be evaluated via video-assisted thoracoscopy (VATS) with a pleural biopsy to enable a definitive histological diagnosis [47]. Similarly, in cases of clinical and/or radiological suspicion of pleural mesothelioma, even in the absence of pleural effusion, histological evaluation via VATS should be pursued. It is important during the biopsy procedure to obtain a sample of the subpleural adipose tissue to assess the invasiveness. If possible, biopsies should be taken from multiple sites. The uniportal surgical approach should, if possible, be positioned at the level of a subsequent thoracotomy to prevent implantation metastases. In patients with a histologically confirmed diagnosis of pleural mesothelioma, a FAPI-PET-CT scan may be performed prior to planned curative surgical therapy [48, 49, 50]. If a PET-CT cannot be performed, a CT scan of the abdomen should be performed in addition to a chest CT, both with contrast medium if possible. A contralateral VATS or laparoscopy should be considered if there is radiological suspicion of contralateral or peritoneal involvement and clinical indications warrant it. To investigate infiltration of the chest wall, particularly the ribs or vertebral bodies, or to assess the presence of transmural diaphragmatic infiltration, a thoracic MRI may be performed if clinically indicated. Prior to planned curative surgical therapy, invasive lymph node staging should be performed using endobronchial ultrasound (EBUS) or, if necessary, mediastinoscopy [51, 52].
figure 3 summarizes the diagnostic approach for suspected pleural mesothelioma.
2 VATS – video-assisted thoracoscopy
3 EBUS – endobronchial ultrasounda) If FAPI PET-CT is not reimbursed, perform a standard chest CT
5.1.2Pathology
The histopathological diagnosis of pleural mesothelioma should be based on a representative tumor specimen and is clearly superior to a diagnosis based solely on cytology, e.g., from a pleural effusion. For differential diagnosis to rule out lung adenocarcinoma, the mesothelioma markers calretinin, mesothelin, cytokeratins 5/6, Wilms tumor 1 (WT-1), and D-240 should be assessed by immunohistochemistry. Likewise, the adenocarcinoma markers TTF1, CEA, and Ber-EP4 should be evaluated for differential diagnosis to adenocarcinoma [53]. The histological subtype of the mesothelioma should be specified, along with a statement regarding the certainty of the diagnosis according to the criteria of the European Mesothelioma Panel [https://www.pathologie-bochum.de/mesotheliom-panel.html].
Molecular pathological analyses, which are firmly established in routine pre-treatment diagnostics for other tumor types, such as NSCLC, are not yet available for routine diagnostics in pleural mesothelioma.
In the prospective registry study of the NCT/DKTK-MASTER program [54], a comprehensive genomic and transcriptomic characterization was performed in patients with pleural and peritoneal mesothelioma. A high prevalence of recurrent alterations in classic tumor suppressor genes (including BAP1, CDKN2A, NF2, SETD2, TP53) as well as in genes involved in homologous recombination (HR), often with evidence of an HR-deficiency signature. Based on these findings, a molecular tumor board was able to identify potential targeted or immuno-oncology treatment strategies in the majority of cases and implement them with clinically relevant benefit in a subset of patients. The data underscore the central role of pathology in the integration of high-throughput molecular techniques (whole-exome/whole-genome sequencing, RNA sequencing) into the diagnosis of mesothelioma.
However, further clinical and preclinical studies are necessary to substantiate the significance of molecular pathological testing in pleural mesothelioma and, if appropriate, to firmly integrate it into the clinical diagnostic process with regulated cost reimbursement. In individual cases, molecular pathological testing may be pursued, for example, through inclusion in a clinical trial or as part of an approved off-label use. This would be particularly the case if a therapeutic option is available based on the molecular pathological findings. At the time of this guideline update (September 2026), however, molecular pathology is not reimbursable in routine clinical practice, at least within the statutory health insurance system, and there are no approved therapeutic options independent of off-label use that depend on the results of molecular pathology.
5.2Classification and Staging
Staging for pleural mesothelioma is based on the IASLC/IMIG analyses in accordance with UICC 9 [55, 56, 57]. The TNM classification is summarized in tables 2 and 3, and the staging is summarized in table 4.
ª Psum = pmax1 + pmax2 + pmax3 (sum of three measurements of the maximum pleural thickness on axial images along the thoracic wall or mediastinum in the three thoracic segments (upper, middle, lower) defined by two lines: one at the level of the aortic arch, the second at the level of the left atrium).
ᵇ Fmax = maximum thickness of the pleural tumor along the fissures, measured in sagittal images.
N Category | Clinical (cN) and pathological (pN) N descriptors | M Category | Clinical M descriptor (cM) |
|---|---|---|---|
NX | Regional lymph nodes cannot be assessed | M0 | No distant metastases |
N0 | No regional lymph node metastases | M1 | Distant metastases present |
N1 | Metastases in ipsilateral intrathoracic lymph nodes (including ipsilateral bronchopulmonary, hilar, subcarinal, paratracheal, aortopulmonary, paraesophageal, peridiaphragmatic and internal mammary lymph nodes) | ||
N2 | Metastases in contralateral lymph nodes; metastases in ipsilateral or contralateral supraclavicular lymph nodes |
N0 | N1 | N2 | |
|---|---|---|---|
T1 | I | II | IIIA |
T2 | II | IIIA | IIIA |
T3 | IIIA | IIIA | IIIA |
T4 | IIIB | IIIB | IIIB |
M1 | IV | IV | IV |
6Therapy
6.1Treatment Structure
Treatment for pleural mesothelioma depends on the stage and histological subtype. The patient’s general condition and comorbidities must be taken into account when selecting a treatment and determining the treatment plan. Given that patients are often at a very advanced age, a geriatric evaluation should always be performed. This should be done early on, particularly when a perioperative approach is being considered. The overall treatment plan should be established by a multidisciplinary tumor board at a facility experienced in all treatment options - preferably a DKG-certified mesothelioma center, if possible.
An algorithm for the treatment of pleural mesothelioma is shown in figure 4.
2 For carefully selected patients (see chapter 6.1.1), assessment based on imaging and consultation with the multidisciplinary tumor board; treatment plan developed at a center with extensive experience.
3 (e)P/D - extended pleurectomy and decortication
4 Depending on clinical symptoms and disease progression
5 PD - progressive disease
6 Off-label use - drug not approved for this indication
7 Only in justified individual cases, such as intolerance to CTLA-4 immune checkpoint inhibitors
8 In Switzerland, nivolumab and ipilimumab are approved for epithelioid histology only if PD-L1 expression is ≥ 1%
9 In Switzerland, bevacizumab for PD-L1-negative epithelioid histology is generally covered by SUVA as approved off-label use. However, a prior application for cost coverage is required. See chapter 6.1.2.
curative intent; palliative intent
6.1.1First-Line Therapy in the Potentially Resectable Stage with Epithelioid Histology and Patients in Good General Condition Without Relevant Risk Factors
Systemic therapy plays a particularly important role in the treatment of pleural mesothelioma, as complete resection of the tumor is practically impossible even in localized stages; therefore, treating systemic micrometastases is crucial for achieving the best possible long-term prognosis.
The first evidence of the efficacy of a combination therapy consisting of cisplatin and pemetrexed, administered over a median of 6 cycles, was demonstrated in a phase III study of unresectable patients by Vogelzang et al., showing an improvement in overall survival (OS) from 9.3 to 12.1 months (HR: 0.77; p-value = 0.02), as well as progression-free survival (PFS) of 5.1 vs. 3.9 months (p-value = 0.001), and a response rate of 41.3% vs. 16.7% (p-value < 0.0001) [58]. Since then, the neoadjuvant or adjuvant administration of 4 cycles of cisplatin and pemetrexed has become an empirically and clinically recognized standard of care.
If there are contraindications to cisplatin and/or pemetrexed, pemetrexed can be replaced, for example, with vinorelbine or gemcitabine, and in cases of clear contraindications to cisplatin, it can be substituted with carboplatin if indicated [59, 60, 61].
The goal of surgical resection is the macroscopically complete removal of the tumor to achieve the maximum possible cytoreduction. The indication for surgical resection should be determined for very carefully selected patients at an experienced center. Only patients with an epithelioid subtype without lymph node involvement, in good general health (ECOG 0-1), at a (very) early stage of disease, and without significant comorbidities should be selected for a multimodal approach consisting of surgical resection accompanied by neoadjuvant or adjuvant chemotherapy.
In the British multicenter phase III MARS 2 trial [62], patients with resectable pleural mesothelioma were randomized after two cycles of induction chemotherapy with platinum/pemetrexed to receive either (extended) pleurectomy/decortication followed by chemotherapy or continued chemotherapy alone. The primary endpoint was OS from the time of randomization. OS was significantly worse in the surgery arm (median OS 19.3 vs. 24.8 months; negative difference in restricted mean survival time at 2 years of 1.9 months; p=0.019). Significantly more severe adverse events (grade ≥ 3) and postoperative complications occurred in the surgery arm. Perioperative morbidity and mortality were higher than in the chemotherapy arm, and quality of life was impaired in the short term in the surgery arm, with no benefit observed in the long term.
The pragmatic design, which included numerous centers with varying levels of surgical experience, led to considerable heterogeneity in surgical quality and perioperative care. Patient selection was suboptimal, with a significant proportion of non-epithelial tumors or tumors subsequently classified as biphasic, as well as locally advanced (in some cases metastatic) stages and patients who had experienced disease progression during neoadjuvant therapy. Traditionally, little benefit from surgical therapy is expected for these patient groups. Commentaries emphasize that the results argue against routine radical surgical cytoreduction in unselected populations but should not be interpreted as a general contraindication for surgery in highly selected patients at experienced centers. The authors of this guideline interpret the results of the MARS 2 study such that, given the criticisms outlined, no general contraindication against surgery can be derived from them [63]. However, the study underscores the importance of strict patient selection for a treatment plan involving surgery [63].
Today, the surgical procedure of choice is considered to be extended pleurectomy/decortication ((e)P/D), i.e., the complete removal of the parietal and visceral pleura while preserving the lung parenchyma, supplemented, if necessary, by diaphragmatic and/or pericardial resection. Preservation of the diaphragm results in fewer postoperative complications, improved postoperative quality of life, and shorter surgical time and hospital stay without reducing overall survival [64, 65]. The extrapleural pneumonectomy (EPP) procedure is considered obsolete, even in light of the aforementioned MARS 2 study.
Histological confirmation and staging should be performed as described in chapter 5.1. Patients in good general condition (ECOG 0) with localized stage I-IIIA epithelioid mesothelioma may be offered (e)PD, provided they have adequate pulmonary function, either following neoadjuvant chemotherapy or as primary therapy followed by adjuvant chemotherapy with cisplatin and pemetrexed.
In this context, it should be noted that neoadjuvant chemotherapy consisting of 4 cycles of a platinum-based combination is generally much easier to administer than adjuvant therapy following (e)P/D, in which the dose density usually must be reduced due to postoperative limitations. On the other hand, it should be noted that the postoperative recovery period is generally significantly longer following neoadjuvant chemotherapy.
Based on the available study data, no evidence can be derived to support a general preference for neoadjuvant over adjuvant chemotherapy. A randomized phase II study (EORTC-1205) [66] found no evidence of a clinical benefit for either treatment sequence. The timing of systemic therapy should therefore be determined on an individual basis by a multidisciplinary tumor board, taking patient preferences into account.
The treatment goal of the combination of surgical cytoreduction and systemic therapy is to achieve the longest possible disease control while maintaining a good quality of life. A formally curative treatment approach involving radical (R0) tumor resection is practically impossible in malignant pleural mesothelioma. In individual cases, long progression-free periods of >10 years can be achieved; however, in the long term, a relapse, usually local, almost always occurs. Depending on the location and extent of the relapse, local therapeutic approaches in combination with systemic therapy may then be offered again if necessary.
The treatment plan should be developed during a multidisciplinary conference at a facility experienced in the treatment of pleural mesothelioma, ideally at a DKG-certified lung cancer center with a mesothelioma unit.
Immune checkpoint inhibitors (ICI) are not yet approved for neoadjuvant or adjuvant use. A phase II study [67] investigated the perioperative use of nivolumab alone or nivolumab in combination with ipilimumab in patients with resectable, epithelioid pleural mesothelioma. The objective was to evaluate the feasibility and safety of neoadjuvant and adjuvant immune checkpoint blockade in conjunction with the planned resection. The dual primary endpoints were “feasibility” (including the proportion of patients who underwent the planned Surgery) and safety. The treatment proved feasible, with a high proportion of surgeries actually performed (over 80% in both arms). In the nivolumab arm, the median disease-free survival (DFS) among patients who underwent surgery was 9.6 months, and the median OS was 19.3 months. In the nivolumab + ipilimumab arm, the median DFS was 19.8 months and the median OS was 28.6 months. The observed adverse events included the typical spectrum of immune-mediated toxicities associated with nivolumab and ipilimumab, including grade 3/4 events, but were generally manageable in the perioperative setting without excessive perioperative mortality. Key limitations include the non-randomized phase II design, the limited number of cases, and the absence of a control arm without immunotherapy. The study should therefore be interpreted primarily as a feasibility and hypothesis-generating study. It is not yet possible to draw conclusions regarding an actual survival benefit compared to established multimodal approaches.
6.1.2First-line Therapy for non-Epithelioid Histology and for Epithelioid Histology in Unresectable or Recurrent Stages
In cases of unresectable disease and/or non-epithelioid histology, therapy consisting of the combination of the ICI nivolumab and ipilimumab is considered the current first-line standard of care. In the randomized phase III CheckMate743 trial, the ICI combination demonstrated significant superiority in OS compared to cisplatin/carboplatin and pemetrexed in patients with non-epithelioid histology, with a 9.3-month extension in median OS (18.1 vs. 8.8 months; HR: 0.46)) [68]. In patients with epithelioid histology, median OS tended to be better, though not statistically significant, compared with treatment with cisplatin/carboplatin and pemetrexed, at 18.7 months in the ICI arm and 16.5 months in the chemotherapy arm (HR: 0.86). For the entire patient population, median OS was also longer in the immunotherapy arm (18.1 vs. 14.1 months; HR: 0.74; p-value = 0.002) than in the chemotherapy arm. Regardless of histological subtype, a retrospective subgroup analysis showed that patients with PD-L1 expression of ≥ 1% on the tumor surface (TPS) benefited more from the immunotherapy combination than patients with PD-L1 expression of < 1% TPS (PD-L1 ≥ 1% TPS: median OS 18.0 vs. 13.3 months (HR: 0.69); PD-L1 < 1% TPS: median OS 17.3 vs. 16.5 months (HR: 0.94)). Due to the retrospective nature of the subgroup analysis and the small number of cases, making a treatment decision based solely on PD-L1 status is not recommended. However, in Switzerland, PD-L1 expression is sometimes relevant with regard to the approval of nivolumab and ipilimumab (see below). Median PFS was comparable across the entire patient population in both study arms (6.8 months in the immunotherapy arm and 7.2 months in the chemotherapy arm (HR: 1.00)). However, progression occurred more frequently in the ICI arm than in the chemotherapy arm during the first 6 months [68]. The median duration of response in the overall patient population was 11.0 months in the ICI arm and 6.7 months in the chemotherapy arm, meaning that patients benefited from a response to ICI therapy for a longer period. In both study arms, the objective response rate was comparable, at 40% in the ICI arm and 43% in the chemotherapy arm.
In the CheckMate 743 study, the ICI arm demonstrated better control of disease-related symptoms—anorexia (HR: 0.51), fatigue (HR: 0.43), pain (0.55), dyspnea (HR: 0.75), and cough (HR: 0.78), as well as a better overall quality of life, as measured by the standardized questionnaires LCSS-Meso ASBI (HR: 0.52) and LCSS-Meso 3-IGI (HR: 0.61) [68, 69]. Since the study met its primary endpoint (improvement in OS across the entire study population), patients may benefit from the possibility of a longer-lasting treatment response, and since symptom control and quality of life were more favorable in the checkpoint inhibitor arm, treatment with nivolumab and ipilimumab can be considered a potential treatment option for both histological subtypes.
In a retrospective, multicenter registry analysis conducted at 12 German cancer centers, the combination of nivolumab and ipilimumab showed comparable results in patients potentially eligible for the study as in the CheckMate 743 trial; however, the results were poorer in the overall study population [60]. Of particular interest was the finding that patients with (low-grade) immune-mediated adverse events had a better outcome [70].
In Switzerland, the combination of nivolumab and ipilimumab is approved for non-epithelioid histology regardless of PD-L1 status; for epithelioid histology, however, it is approved only for PD-L1 expression with a TPS of ≥1%. In clinical practice in Switzerland, in cases of epithelioid histology with negative PD-L1 expression, submitting an application for coverage of treatment with bevacizumab (in combination with platinum and pemetrexed) is a common procedure. The approval rate for such applications by SUVA is relatively high in Switzerland. For data on bevacizumab, please refer to the following section of this chapter as well as to chapter 6.4.1.1.
However, for patients with a high need for treatment and remission and epithelioid histology, treatment with cisplatin and pemetrexed should continue to be used as the standard of care based on the data presented above [68]. Similarly, patients with a contraindication to ICI therapy should also receive cisplatin and pemetrexed as first-line therapy, provided there are no contraindications to this regimen [68].
In the randomized phase III study IND.227 [71], the combination of pembrolizumab and platinum-based pemetrexed chemotherapy was compared with platinum plus pemetrexed therapy alone in previously untreated patients with advanced pleural mesothelioma. The primary endpoint was OS. The pembrolizumab combination demonstrated a survival benefit (median OS 17.3 vs. 16.1 months; hazard ratio 0.79; p=0.0324; however, the hazard ratio did not meet the threshold for statistical significance) as well as a higher 3-year survival rate (25% vs. 17%). The survival benefit was most pronounced in the group with non-epithelioid mesotheliomas (median OS 12.3 vs. 8.2 months in favor of the pembrolizumab arm; HR: 0.57). For the group with epithelioid mesotheliomas, the median OS in the chemotherapy arm was 18.2 months compared with 19.8 months in the pembrolizumab arm (HR: 0.89). Thus, the survival benefit observed in the overall patient population in the pembrolizumab arm is primarily attributable to the benefit in the group with non-epithelioid mesotheliomas. Grade 3/4 adverse events and treatment-related hospitalizations occurred more frequently in the pembrolizumab arm than with chemotherapy alone. Isolated cases of treatment-related deaths were reported. The toxicity profile was consistent with the known combination of platinum-based chemotherapy and PD-1 blockade, featuring hematologic toxicities and immune-mediated events. Due to the clear survival benefit observed in the non-epithelioid mesothelioma group, pembrolizumab in combination with platinum and pemetrexed was approved in Germany for patients with non-epithelioid mesothelioma. When examining the OS data for epithelioid and non-epithelioid histologies, it is notable that dual checkpoint inhibition in the Checkmate 743 study (nivolumab + ipilimumab) showed comparable results for both histologies (non-epithelioid/epithelioid: 18.1/18.7 months). In the IND.227 study, the pembrolizumab arm showed numerically better median OS for the epithelioid histology than for the non-epithelioid histology (19.8 vs. 12.3 months). This suggests that monotherapy with an ICI in non-epithelioid mesothelioma may not be able to compensate for the low efficacy of chemotherapy in this patient group. For this reason, the use of nivolumab and ipilimumab within the scope of the existing approval is primarily recommended for non-epithelioid histology. If there are contraindications to ipilimumab but not to a PD-1 inhibitor, treatment with platinum, pemetrexed, and pembrolizumab should be considered.
The PD-L1-targeted ICI durvalumab was evaluated in the open-label, multicenter phase III DREAM3R trial [72] for pleural mesothelioma. In this trial, patients with untreated, advanced pleural mesothelioma were randomized in the first-line setting to receive durvalumab in combination with platinum/pemetrexed or platinum/pemetrexed chemotherapy alone. The primary endpoint was OS. The study was terminated early due to slow recruitment, with a significantly lower number of cases than planned. Numerical advantages were observed in favor of the durvalumab combination in terms of median OS, median PFS and objective response rates (median OS 21 vs. 18 months, HR 0.92, median PFS 8 vs. 7 months, HR 0.7, objective response rate 58% vs. 35%); however, these differences were not statistically significant for median OS and PFS. The adverse event profile was consistent with that of a combination of platinum/pemetrexed chemotherapy and PD-L1 inhibition, with expected hematologic and immune-mediated toxicities. Serious treatment-related adverse events were more frequent in the combination arm than with chemotherapy alone, but remained manageable overall. The main limitation of the study is its premature termination with a significantly smaller number of patients than planned, which considerably limits the statistical power needed to reliably assess a survival benefit. Furthermore, the open-label design is susceptible to bias in the assessment of endpoints and subsequent therapies, and changes in standard of care during the study period (introduction of ipilimumab/nivolumab) complicate interpretation in the context of current treatment algorithms. As of the date of this guideline update (September 2026), durvalumab is not approved in Germany for pleural mesothelioma.
Atezolizumab, another ICI that targets PD-L1, was evaluated in the BEAT-meso study [73] for pleural mesothelioma. In this randomized phase III trial, first-line therapy with carboplatin/pemetrexed and bevacizumab, with or without atezolizumab, was investigated in patients with advanced pleural mesothelioma. The primary endpoint was OS. The primary endpoint was not met (median OS 20.5 vs. 18.1 months; HR 0.84; p=0.14), while PFS was significantly longer in the atezolizumab arm (9.2 vs. 7.6 months; HR 0.72; p=0.0021). Exploratory analyses revealed a marked OS benefit for non-epithelioid histology (OS-HR 0.51), but not for epithelioid tumors (OS-HR 1.01). Grade ≥3 adverse events were more common in the atezolizumab arm (55% vs. 47%), with the toxicity profile reflecting that of intensified chemo-anti-VEGF immunotherapy. Quality of life remained comparable overall between the arms. Since the primary endpoint of OS was not met, the regimen, in the absence of approval, cannot be recommended as a treatment option for the overall population or the non-epithelioid subgroup. The post hoc-identified subgroup superiority in non-epithelioid tumors is exploratory and requires prospective confirmation. The complexity and cost of a triple combination (chemotherapy + bevacizumab + atezolizumab) are offset by only limited additional benefit.
The eVOLVE-Mesostudy (phase III) is evaluating the bispecific antibody volrustomig (anti-PD-1 and anti-CTLA-4) in combination with platinum and pemetrexed in untreated pleural mesothelioma patients against “investigator’s choice” therapy (either nivolumab and ipilimumab or platinum and pemetrexed). The analysis of the study and the final results are pending (NCT06097728).
Pegargiminase (also known as ADI-PEG 20) is an enzyme-based drug that specifically breaks down arginine in the body. It is used to treat tumors that lack the enzyme arginine succinate synthetase 1 (ASS1), since these cancer cells rely on an external supply of arginine to survive. It was investigated in the ATOMIC-Meso study in patients with pleural mesothelioma. The ATOMIC-Meso study [74] is a phase II/III study in chemotherapy-naive patients with non-epithelioid pleural mesothelioma, in which an arginine-depleting therapy with pegargiminase (ADI-PEG20) plus pemetrexed/platinum was compared to placebo plus pemetrexed/platinum. The primary endpoint of the phase III component was OS. The combination with pegargiminase resulted in a significant prolongation of median OS (9.3 vs. 7.7 months; HR 0.71; p=0.02) and PFS (6.2 vs. 5.6 months; HR 0.65; p=0.02). A higher rate of grade 3/4 adverse events was observed in the pegargiminase arm. The spectrum included, in particular, hematologic toxicities and common treatment-related events that require close monitoring. The survival benefit is quantitatively limited and has not yet been translated into broad approval, which restricts its practical availability. The study is limited to non-epithelioid histologies. Therefore, it is not applicable to epithelioid tumors. Although biomarker-guided selection (e.g., ASS1 status) is biologically plausible, it has not yet been widely implemented in routine clinical practice. As of the date of this guideline update (September 2026), pegargiminase is not approved in the EU, Switzerland, the United Kingdom or North America. An application for approval has been submitted to the U.S. Food and Drug Administration (FDA), which had not yet been decided upon at the time of the guideline update. The European Medicines Agency (EMA) granted the active ingredient orphan drug designation at an early stage [75].
For patients with very significant comorbidities, a severely compromised general condition, or those who refuse treatment, it may be appropriate, as part of a joint, individualized decision between the patient and the treating physician, to forgo active tumor therapy and instead pursue a purely palliative approach of “best supportive care.” However, this is always an individual decision for which no generally applicable recommendations can be made due to a lack of randomized data.
6.1.3Second-line and Subsequent Systemic Treatment Options
At the time of this guideline update (September 2026), there are no evaluated randomized phase II or III studies on treatment options following disease progression during first-line therapy with ICIs.
For patients who have not received treatment with nivolumab and ipilimumab as first-line therapy in an inoperable disease setting, treatment with nivolumab and ipilimumab should be considered for “off-label use” based on data from the CheckMate743 study [69], provided there are no contraindications. To ensure reimbursement of costs, an application must be submitted to the health insurance provider.
In cases of disease progression during or after treatment with ipilimumab and nivolumab, treatment with cisplatin and pemetrexed should be administered for up to six cycles; a potential OS of 12.1 months has been reported for this regimen in first-line therapy [58]; see chapter 6.1.1. In a randomized phase II trial (CALGB 30901), maintenance therapy with pemetrexed showed no clinically relevant or statistically significant benefit in terms of PFS or OS [76] and cannot currently be recommended. Switch maintenance therapy with gemcitabine following first-line therapy with platinum and pemetrexed demonstrated an extension of median PFS from 3.2 to 6.2 months compared with best supportive care (HR: 0.44; p-value <0.0001) [77]. However, the data are not robust enough to support a general recommendation for switch maintenance therapy with gemcitabine.
Re-exposure to pemetrexed upon disease progression showed, in patients who had responded to first-line therapy with platinum and pemetrexed for at least 6 months, a disease control rate of 66% in a multicenter retrospective analysis, with a reduction in pain in 43% of patients, a time to progression of 5.1 months, and an overall survival of 13.6 months [78]. Another multicenter, retrospective analysis [74] showed, for patients pretreated with pemetrexed, a disease control rate of 70.7%, PFS of 6.2 months, and OS of 10.6 months upon re-treatment with pemetrexed. As part of this retrospective analysis, patients who had been previously treated with pemetrexed also received second-line therapy consisting of pemetrexed and a platinum derivative [79]. The group of patients who had been retreated with platinum and pemetrexed achieved, compared to those treated with pemetrexed as a single agent, achieved a longer median OS (13.4 vs. 4.2 months; p-value <0.001) and a longer median progression-free survival (6.4 vs. 2.4 months; p = 0.003).
A case series involving four patients who had been treated with platinum and pemetrexed as first-line therapy reported partial remission and three cases of stable disease following re-treatment with platinum and pemetrexed [80].
Another case series reported PFS of 5.0 and 8.2 months in four comparable patients who responded to re-treatment with platinum and pemetrexed [81]. A single-arm observational study involving 31 patients who had been retreated with, among other agents, platinum and pemetrexed (16 patients) (second or subsequent line of therapy) showed a median OS of 10.5 months and a median PFS of 3.8 months [81]. The duration of PFS and OS correlated with the duration of response to first-line therapy with platinum and pemetrexed [82].
Thus, in patients who achieved a response or disease stabilization lasting at least 6 months following therapy with platinum and pemetrexed, re-exposure to pemetrexed, either as a single agent or in combination with a platinum derivative, may be considered in the event of disease progression. In this context, the decision as to whether treatment should be administered as monotherapy or combination therapy should be based on the presence of adverse effects from the previous line of therapy, such as polyneuropathy or hearing loss, as well as on comorbidities and the patient’s general condition.
For patients who have achieved a treatment response or disease stabilization lasting less than 6 months while on platinum and pemetrexed therapy, or who cannot receive pemetrexed therapy due to contraindications, treatment with vinorelbine or gemcitabine should be administered as monotherapy or in combination [83, 84, 85, 86, 87, 88]. The advantages or disadvantages of combination therapy compared to monotherapy have not been explored by randomized data.
In the randomized phase II VIM trial, oral vinorelbine plus active symptom management resulted in a statistically significant improvement in PFS of 4.2 versus 2.8 months compared with active symptom management alone [HR 0.60; p = 0.002] [87].
For vinorelbine, two retrospective analyses in the second or later lines of therapy reported a median PFS of 1.7 and 2.3 months and a median OS of 5.4 and 6.2 months [83, 84].
In a retrospective analysis, gemcitabine monotherapy in the second or later lines of treatment yielded a PFS of 1.6 months and a median OS of 4.9 months [78].
The randomized phase II RAMES trial compared gemcitabine plus placebo with a regimen consisting of gemcitabine and the anti-VEGFR2 antibody ramucirumab in second-line therapy [85]. In this study, the median OS for gemcitabine plus placebo was 7.5 months, compared with 13.8 months in the gemcitabine plus ramucirumab arm (HR: 0.71; p = 0.028). In the gemcitabine/ramucirumab arm, the median PFS was 8.3 months compared with 6.6 months in the gemcitabine/placebo arm (HR: 0.79; p = 0.12).
However, as of the date of this guideline update (September 2026), ramucirumab is not approved for pleural mesothelioma in Germany, Austria, or Switzerland (off-label use).
The randomized phase III ETOP9-15 trial (PROMISE-Meso trial) compared a chemotherapy arm, in which patients received either gemcitabine or vinorelbine (selected by the investigators), with the PD-1 inhibitor pembrolizumab [87]. The median PFS was 3.4 months in the gemcitabine or vinorelbine arm compared with 2.5 months in the pembrolizumab arm (HR: 1.06; p = 0.76). A median OS of 12.4 months was reported in the gemcitabine or vinorelbine arm, compared with 10.7 months in the pembrolizumab arm (HR: 1.12; p = 0.59).
The single-arm phase II PEMMELA study [89] evaluated the combination of pembrolizumab and the multi-tyrosine kinase inhibitor lenvatinib in patients with pleural mesothelioma whose disease had progressed following platinum-based pemetrexed chemotherapy and who had not received prior immunotherapy. The primary endpoint was the objective response rate according to modified RECIST criteria (Response Evaluation Criteria in Solid Tumors). A high response rate of 58% (local assessment; 45% in the independent review) was observed in a total of 38 evaluable patients. The combination was associated with significant toxicity: common grade ≥3 adverse events included hypertension (21%), anorexia, and lymphopenia (11% each), as well as one treatment-related death due to myocardial infarction. In 76% of patients, at least one dose reduction or interruption of lenvatinib was required, underscoring its limited tolerability. The single-arm design without a control group does not allow for a definitive conclusion regarding superiority over standard second-line therapies. The study population is small and selected (single center, ECOG 0-1, no prior immunotherapy), so the generalizability is limited, particularly to the current setting of patients previously treated with ICIs. The pronounced toxicity restricts its use, especially in older patients and those with comorbidities.
For the anthracyclines doxorubicin and epirubicin, efficacy has been reported in patients with unresectable pleural mesothelioma [89, 90, 91, 92]. Due to the availability of more effective agents with a stronger body of clinical evidence, doxorubicin or epirubicin are now administered in clinical practice, if at all, only as monotherapy in advanced stages of treatment following failure of ICIs, platinum derivatives combined with pemetrexed, gemcitabine, and vinorelbine.
In two phase III trials in first-line therapy, doxorubicin demonstrated a median OS of 8.2 and 10 months [80, 82]. In two single-arm phase II trials in first-line therapy, epirubicin demonstrated a median OS of 7.5 and 10 months, as well as response rates of 5% and 15% [93, 94].
Due to the limited efficacy of treatment options in second-line and subsequent lines of therapy for pleural mesothelioma, enrollment of patients in clinical trials is generally recommended.
6.1.3.1Supplementing Systemic Therapy with Tumor Treating Fields (TTF)
Tumor Treating Fields (TTF) is a non-invasive technology that uses local arrays placed on the body surface to apply alternating electric fields with a frequency of approximately 150 kHz to the area of the pleural mesothelioma. This disrupts the spindle apparatus in tumor cells during mitosis. The cell cycle of healthy cells is generally not significantly affected by TTF. The devices have received CE certification in Germany. In a single-arm phase II study (Stellar), patients with inoperable pleural mesothelioma treated with TTF in combination with first-line therapy consisting of cisplatin/carboplatin and pemetrexed achieved a median OS of 18.2 months [95]. The most common side effects documented in the study following TTF administration were skin irritations [95].
As of the date of this guideline update (September 2026), it is unclear whether health insurance companies under the German statutory health insurance (GKV) system will reimburse the costs; however, patients can receive TTFields therapy in addition to systemic therapy as part of the TIGER Meso registry study (NCT05538806). It is also possible to submit a claim to health insurance companies under the GKV system for coverage of TTF therapy as an adjunct to systemic therapy. To ensure a smooth process, it is recommended that the individual claim for TTF reimbursement for patients insured under UVT be approved by the relevant tumor board as appropriate for the treatment of the individual patient, and that this consensus be documented in writing in the claim. In an interim analysis of the TIGER Meso study conducted in the summer and fall of 2025, no new safety signals were documented with the addition of TTFields to systemic therapy (primarily nivolumab plus ipilimumab). The adverse event profile observed in the Stellar study was confirmed. Due to the currently limited data available, no clear recommendation can yet be made regarding the role of TTF within the current multidisciplinary therapeutic spectrum.
6.2Surgery/Surgical Procedures
Surgical procedures are used for diagnosis (see chapter 5.1) and in the treatment of patients with the epithelioid subtype who are in good general health and at an early stage of the disease. In cases of non-epithelioid pleural mesothelioma, surgical procedures beyond diagnostic purposes should be limited to individualized treatment plans following a decision by a multidisciplinary tumor board at an experienced center. Therapeutic surgical procedures should be performed as extended pleurectomy and decortication ((e)PD). The indication for surgical therapy should be supported by a multidisciplinary tumor board and performed at experienced centers. Surgical procedures intended for therapeutic purposes should be accompanied by four (to five) cycles of systemic therapy consisting of cisplatin and pemetrexed administered neoadjuvantly or adjuvantly (57, 65) (see chapter 6.1.1).
6.3Radiotherapy
Radiotherapy is effective for palliative treatment of pleural mesothelioma and is of particular clinical importance in cases of tumor infiltration of the spine. It should be administered in a timely manner before the onset of spinal symptoms. In larger retrospective studies and one prospective study, partial remissions of pain symptoms were observed in approximately 50% of patients as early as 2 weeks after radiation therapy [94, 95]. Effective dosages are 10-12 × 3 Gy per fraction, 5 fractions per week, or 4 Gy per fraction up to a total dose of at least 20 Gy. Objective reductions in the size of pleural mesothelioma lesions, as defined by partial remission according to RECIST, were observed in 45% of patients at a dose of 12 × 3 Gy per week or a higher effective dose [96, 97]. In sarcomatoid pleural mesotheliomas, lower response rates were observed compared to epithelioid mesotheliomas [97]. On the other hand, radiation therapy has been reported to be particularly effective in biphasic pleural mesothelioma with a high proportion of sarcomatoid components [98].
The use of radiotherapy for oligoprogression in up to 3 sites following first-line therapy has been investigated in retrospective studies. This focal radiation therapy, often performed using stereotactic techniques, results in local tumor control rates of 75% after one year when administered at an adequate dose; thus, its use in cases of localized oligoprogression can be recommended as an individualized treatment option on a case-by-case basis [99, 100].
More recently, radiation therapy of the ipsilateral pleural space following pleurectomy/decortication has been studied using intensity-modulated radiation therapy while adhering to strict dose-volume limits for the lungs [101, 102]. In a randomized Italian study involving 108 patients, a survival benefit was found with the early use of pleural cavity irradiation up to 50 Gy in conventional fractionation following pleurectomy/decortication and chemotherapy, compared to palliative low-dose-rate radiotherapy. All patients in this study still had a macroscopic residual tumor postoperatively, to which an additional boost of up to 60 Gy was applied using the simultaneously integrated technique. Distant metastases and contralateral mediastinal lymph nodes were exclusion criteria for this study [103]. Pleural space irradiation has proven to be safely feasible in experienced centers. However, before this challenging technique is widely adopted outside of clinical trials, the results of the randomized NRG-Oncology Group study (NRG-LU-006) on this treatment modality should be awaited.
Since EPP is no longer used as part of standard of care, radiotherapy of the affected hemithorax in addition to EPP has only limited potential. It can be used postoperatively following macroscopically complete resection but should only be performed at experienced centers with strict adherence to safety margins for surrounding organs. In a single-arm phase II study (SMART) [103], 96 patients with histologically confirmed, resectable, previously untreated pleural mesothelioma received hemithorax radiation at 25 Gy (with a 5 Gy boost to high-risk areas) followed by EPP. In cases of lymph node involvement, adjuvant chemotherapy was offered. 49% of patients experienced a grade 3-4 adverse event within the first 30 days after surgery. The cumulative 5-year incidence of distant recurrence was 63.3%.
In the previous period, radiation therapy to the access sites following thoracotomy, thoracoscopy, or the placement of larger pleural drains was performed more frequently. However, according to recent prospective studies, the incidence of implantation metastases in the access sites is only about 15% after 18 months. Given the high competing risks of tumor progression at other sites, the benefit of adjunctive radiation therapy to the access sites was negligible in the randomized trials conducted, so its use is not recommended.
6.4Systemic Tumor Therapy
6.4.1Systemic Agents in Alphabetical Order
6.4.1.1Bevacizumab
In a phase III study, bevacizumab as first-line therapy in combination with cisplatin and pemetrexed improved OS in patients with unresectable pleural mesothelioma by 2.7 months compared with cisplatin and pemetrexed without bevacizumab (18.8 vs. 16.1 months; HR: 0.77, p = 0.0167) [104]. In a retrospective single-center analysis, the addition of bevacizumab to induction chemotherapy with platinum and pemetrexed in patients with resectable pleural mesothelioma significantly improved the overall response rate according to mRECIST compared with induction therapy with platinum and pemetrexed alone (p = 0.046) [105, 106]. When combined with carboplatin, pemetrexed, and atezolizumab, the addition of bevacizumab was beneficial in terms of median OS for patients with non-epithelioid pleural mesothelioma ([73] see chapter 6.1.2). Bevacizumab is not approved in the EU for this indication. In Switzerland, bevacizumab is very frequently accepted by SUVA for off-label use following a request for coverage.
6.4.1.2Carboplatin
If there are clear contraindications to cisplatin, carboplatin may be administered in neoadjuvant, adjuvant, or palliative settings; see chapter 6.1.1 and chapter 6.1.3, as applicable [61]. Possible combination partners include pemetrexed, vinorelbine, or gemcitabine. When combined with gemcitabine, the pronounced myelotoxic effect, which carries an increased risk of severe anemia and thrombocytopenia, must be taken into account. Common side effects of carboplatin include nausea and vomiting, as well as anemia, thrombocytopenia, and leukopenia.
6.4.1.3Cisplatin
Cisplatin in combination with pemetrexed represents the current standard of care in the neoadjuvant or adjuvant setting; see chapter 6.1.1 [58]. In unresectable cases, if there are contraindications to ICIs or in the presence of epithelioid histology and remission pressure, the combination of cisplatin and pemetrexed may be used as first-line therapy [57], or it may be administered as second-line therapy following progression on first-line therapy with checkpoint inhibitors; see chapter 6.1.3 [58] if applicable. In unresectable cases, cisplatin as a single agent achieved a median OS of 9.3 months, compared with 12.1 months when combined with pemetrexed, and a response rate of 16.7% (single agent) versus 41.3% (in combination with pemetrexed) [58]. Common side effects of cisplatin include nausea and vomiting, as well as anemia, thrombocytopenia, and leukopenia. There is also a risk of neurological side effects, such as hearing loss and polyneuropathy. Due to potential nephrological side effects, renal function should be monitored during therapy, and adequate hydration should be ensured during administration. If necessary, tolerability can be improved by administering a split dose (2-3 divided doses), as demonstrated in studies on non-small-cell lung cancer.
6.4.1.4Doxorubicin (Adriamycin)
The anthracycline doxorubicin demonstrated a median OS of 8.2 and 10 months in two randomized phase III trials in first-line therapy [90, 91]. Due to the availability of more effective agents with stronger evidence from clinical trials, doxorubicin is now administered in clinical practice, if at all, only as monotherapy in advanced stages of the disease following failure of immune checkpoint inhibitors, platinum-based agents, gemcitabine, and vinorelbine. Common side effects include nausea and vomiting, as well as anemia, thrombocytopenia, and leukopenia. Cardiac toxicity must also be closely monitored. Due to the risk of tissue necrosis from extravasation, care must be taken to ensure a secure venous access site during administration.
6.4.1.5Epirubicin
The anthracycline epirubicin demonstrated a median OS of 7.5 and 10 months and a response rate of 5% and 15% in two single-arm phase II studies in first-line therapy [90, 92]. Due to the availability of more effective agents with stronger clinical evidence, epirubicin is now administered in clinical practice, if at all, only as monotherapy in advanced stages of treatment following failure of immune checkpoint inhibitors, platinum derivatives, gemcitabine, and vinorelbine. Common side effects include nausea and vomiting, as well as anemia, thrombocytopenia, and leukopenia. Cardiac toxicity must also be closely monitored. Due to the risk of tissue necrosis from extravasation, care must be taken to ensure a secure venous access site during administration. Epirubicin is not approved for this indication in the EU.
6.4.1.6Gemcitabine
Gemcitabine can be administered as a single agent or in combination with platinum derivatives or vinorelbine in the second-line setting or in a subsequent line of therapy; see chapter 6.1.3. As monotherapy in the second-line and subsequent treatment lines, gemcitabine achieved a median OS of 4.9-12.4 months [83, 84, 85]; see chapter 6.1.3. Common side effects of gemcitabine include nausea and vomiting, as well as anemia, thrombocytopenia, and leukopenia.
6.4.1.7Ipilimumab
In combination with nivolumab, the anti-CTLA-4 ICI ipilimumab is approved as a first-line systemic therapy for unresectable disease. In this setting, ipilimumab in combination with nivolumab demonstrated a 4-month prolongation of median overall survival compared with combination therapy with platinum and pemetrexed (18.1 vs. 14.1 months; HR: 0.74; p = 0.002) [69]. For information on differentiated use and study data, see chapter 6.1.2. Common side effects of ICIs include fatigue, pruritus, hypo- or hyperthyroidism, and diarrhea. In addition, autoimmune inflammatory reactions such as pneumonitis, colitis, nephritis, hepatitis, hypophysitis, myositis, cardiomyopathy, and arthralgia may occur in rare cases.
6.4.1.8Nivolumab
Nivolumab is an anti-PD-1 ICI. Data on approved indications, clinical trial data, and possible side effects are presented in chapter 6.4.1.7 and chapter 6.1.2. As of September 2026, it is not approved for use as monotherapy. To ensure coverage of costs, an application must be submitted to the health insurance provider (accident insurance provider or health insurance provider).
6.4.1.9Pembrolizumab
Pembrolizumab is an anti-PD-1 ICI and is approved in combination with platinum and pemetrexed for first-line treatment of non-epithelioid pleural mesothelioma [71]; see chapter 6.1.2. Compared with treatment with cisplatin and pemetrexed, it significantly improved median OS (17.3 vs. 16.1 months; HR 0.79; p = 0.0324). This effect was primarily driven by non-epithelioid mesotheliomas. It can be assumed that PD-1 checkpoint inhibition alone appears to have a weaker effect on non-epithelioid mesotheliomas than dual checkpoint inhibition consisting of anti-PD-1 and anti-CTLA-4 (see chapter 6.1.2). For this reason, the combination of pembrolizumab + platinum + pemetrexed is not the primary recommendation of this guideline for non-epithelioid pleural mesothelioma (see chapter 6.1.2).
6.4.1.10Pemetrexed
Pemetrexed can be administered neoadjuvantly or adjuvantly in combination with a platinum derivative [51]. It can also be used in unresectable cases in combination with a platinum derivative or as monotherapy when contraindications exist [58, 67]; see chapter 6.1.3. In unresectable cases, the addition of pemetrexed to cisplatin, compared with cisplatin monotherapy, improved median OS from 9.3 to 12.1 months and PFS from 5.1 to 3.9 months, and resulted in a response rate of 41.3% versus 16.7% [67], see chapter 6.1.1 and chapter 6.1.3. According to the approval, supportive concomitant therapy with folic acid and vitamin B12 must be administered. Possible side effects include nausea and vomiting, as well as anemia, thrombocytopenia, leukopenia, stomatitis, mucositis, and renal damage.
6.4.2Vinorelbine
Vinorelbine is a vinca alkaloid and can be administered as monotherapy or in combination with gemcitabine in the second-line setting or in subsequent lines of therapy; see chapter 6.1.3. Vinorelbine, when used as monotherapy in the second-line or later treatment lines, can achieve a median OS of 5.4-12.4 months [64, 65, 67, 68]; see chapter 6.1.3. Common side effects of vinorelbine include anemia, thrombocytopenia, leukopenia, and polyneuropathy.
7Rehabilitation
Following completion of curative or palliative therapy, in the absence of signs of relapse or disease progression and when there is no acute indication for further treatment, rehabilitation measures may be implemented to improve physical endurance, particularly cardiopulmonary function, and to manage potential treatment side effects. A request for rehabilitation must be submitted to the appropriate health insurance provider, either the workers’ compensation insurance provider or the health insurance provider.
8Monitoring and Follow-up
During systemic therapy, radiological monitoring to assess treatment success should be performed every 6-8 weeks using chest and abdominal CT scans. Patients who have undergone resection for pleural mesothelioma should receive follow-up care with chest and abdominal CT scans every three months for a period of two years after completion of therapy. Thereafter, the interval may be extended to six months on an individual basis, depending on the patient’s risk profile.
9References
Galateau-Salle G, Churg A, Roggli V, Travis WD on behalf of the World Health Organization Committee for Tumors of the Pleura. The 2015 World Health Organization Classification of Tumors of the Pleura: Advances since the 2004 Classification. J Thorac Oncol 2016;11:142-154. DOI:10.1016/j.jtho.2015.11.005
Alì G, Bruno R, Fontanini G. The pathological and molecular diagnosis of malignant pleural mesothelioma: a literature review. J Thorac Dis 2018;10(Suppl 2):S276-S284. DOI:10.21037/jtd.2017.10.125
Lehnert M, Kraywinkel K, Heinze E et al. Incidence of malignant mesothelioma in Germany, 2009–2013. Cancer Causes Control 2017;28:97–105. DOI:10.1007/s10552-016-0838-y
DGUV Statistics for Practice 2024, Current Figures and Time Series from the German Social Accident Insurance; https://publikationen.dguv.de/statistiken/
Cancer in Germany: Center for Cancer Registry Data, Robert Koch Institute https://www.krebsdaten.de/krebs/de/content/publikationen/krebs_in_deutschland/kid_2025/kid_2025_c45_mesotheliom
Rheinland-Pfalz Cancer Registry, https://www.krebsregister-rlp.de/fileadmin/user_upload/dokumente/krebsarten/c45; Hessian Cancer Registry
https://hessisches-krebsregister.de/datenauswertung/krebs-in-hessen/inzidenz-und-mortalitaet
Delva F, Gramond C, Thaon I et al. Co-exposure to asbestos, mineral wool, crystalline silica, and refractory ceramic fibers and the risk of lung cancer and mesothelioma. Thorax 2026;81:430–438. DOI:10.1136/thorax-2024-222020
Gi M, Suzuki S, Saleh DM et al. Comparative gene expression analysis of malignant mesothelioma and lung adenocarcinomas induced by multi-walled carbon nanotube-7 and double-walled carbon nanotubes in rats: distinct molecular signatures and canonical pathways. Nanomaterials 2025;15:1806. DOI:10.3390/nano15231806
Lotz G, BAuA - baua: Practice - Occupational Health and Toxicological Guidance for Work Involving Carbon Nanotubes (CNT) - Federal Institute for Occupational Safety and Health; 2015, 1st edition, https://www.baua.de/de/angebote/publikationen/praxis/a94, accessed on July 1, 2026
Attanoos RL, Churg A, Galleteau-Salle F et al. Malignant mesothelioma and its non-asbestos causes. Arch Pathol Lab Med 2018;142:753-760. DOI:10.5858/arpa.2017-0365-RA
Carbone M, Yang H, Pass HI et al. BAP1 and cancer. Nat Rev Cancer 2013;13:153-159. DOI:10.1038/nrc3459
Federal Institute for Occupational Safety and Health, ed.: National Asbestos Profile for Germany. Dortmund, Berlin, Dresden; 2nd ed. 2020. Available at: https://www.baua.de/de/angebote/publikationen/berichte/gd80-3
German Social Accident Insurance. Fiber Years. BK Report 1/2013. Available at: https://publikationen.dguv.de/forschung/ifa/ifa-report/2757/faserjahre-bk-report-1/2013
Peto J, Decarli A, La Vecchia C, Levi F, Negri E. The European mesothelioma epidemic. Br J Cancer 1999;79:666-672. DOI:10.1038/sj.bjc.6690105
Allen LP, Baez J, Stern MEC, Takahashi K, George F. Trends and the economic impact of asbestos bans and the decline in asbestos consumption and production worldwide. Int J Environ Res Public Health 2018;15:531. DOI:10.3390/ijerph15030531
Federal Ministry of Labor: Announcement dated November 8, 1993. Federal Labor Gazette 167:1994
Selikoff IJ. Lung cancer and mesothelioma during prospective surveillance of 1,249 asbestos insulation workers, 1963–1974. Ann N Y Acad Sci 1976;271:448–56. DOI:10.1111/j.1749-6632.1976.tb23146.x
Hosbach I, Weidhass S, Eisenhawer C, Brüning T. BK No. 4105: Mesothelial Tumor or “Benign” Mesothelioma; IPA Journal 2025;03:12-17.
Frei-Stuber L, Tannapfel A, Schellhase HM, Nowak D. Mesothelioma in situ of the parietal pleura as an occupational disease following occupationally insured asbestos exposure—a case report with expert assessment in a social court proceeding [Mesothelioma in situ of the parietal pleura as an occupational disease after exposure to asbestos: a case report of an insured patient with assessment in a social court proceeding]. Pneumologie 2026;80:454-462 (in German). DOI:10.1055/a-2783-4669
German Social Accident Insurance, ed. Recommendations for the Assessment of Asbestos-Related Occupational Diseases—Falkensteiner Recommendations. Berlin; DGUV, 2011. Available at: https://publikationen.dguv.de/versicherungleistungen/berufskrankheiten/2459/empfehlung-fuer-die-begutachtung-asbestbedingter-berufskrankheiten-falkensteiner-empfehlung
Otte N, Fraune E, Cetiner Y et al. Asbestos Surveillance Program Aachen (ASPA): Cancer mortality among asbestos-exposed power industry workers. Lung Cancer 2024;195:107899. DOI:10.1016/j.lungcan.2024.107899
German Social Accident Insurance (DGUV), ed.: Occupationally Induced Cancers. Berlin; DGUV, 2012. Available at: https://publikationen.dguv.de/zahlen-fakten/schwerpunkt-themen/2562/beruflich-verursachte-krebserkrankungen
BK Report 2024; https://www.dguv.de/de/forschung/bk-berichte/index.jsp
DGUV Recommendations for Occupational Health Consultations and Examinations, 2nd edition, 2024; available at https://publikationen.dguv.de/praevention/ausschuss-arbeitsmedizin-aamed-guv-dguv-vorsorge/4783/dguv-empfehlungen-fuer-arbeitsmedizinische-beratungen-und-untersuchungen
https://www.dguv-vorsorge.de/vorsorge/nachgehende_vorsorge/organisation/gvs/index.jsp
Taeger D, Wichert K, Lehnert M et al. Lung cancer and mesothelioma risks in a prospective cohort of workers with asbestos-related lung or pleural diseases. Am J Ind Med 2022;65:652-659. DOI:10.1002/ajim.23401
Hosbach I, Wiethege T, Weber D et al. EVA-Mesothel. Early detection of mesotheliomas. IPA-Journal, 1, 2026, pp. 20–24.
Johnen G, Burek K, Raiko I et al. Prediagnostic detection of mesothelioma by circulating calretinin and mesothelin—a case-control comparison nested within a prospective cohort of asbestos-exposed workers. Sci Rep 2018;8:14321. DOI:10.1038/s41598-018-32315-3
Hasegawa S: Early mesothelioma revisited. Int J Clin Oncol 2012;17:30–32. DOI:10.1007/s10147-011-0365-5
Bertoglio P, Ambrogi MC, Chella A et al. Is less also better? A single-institution experience with the treatment of early-stage malignant pleural mesothelioma. Eur J Surg Oncol 2017;43:1365-1371. DOI:10.1016/j.ejso.2017.02.010
O'Brien ME, Watkins D, Ryan C et al. A randomized trial in malignant mesothelioma (M) comparing early (E) versus delayed (D) chemotherapy in symptomatically stable patients: the MED trial. Ann Oncol 2006;17:270-275. DOI:10.1093/annonc/mdj073
Bintcliffe OJ, Hooper CE, Rider IJ, et al. Unilateral Pleural Effusions with More Than One Apparent Etiology. A Prospective Observational Study. Ann Am Thorac Soc. 2016;13(7):1050-1056. DOI:10.1513/AnnalsATS.201601-082OC
Arnold DT, De Fonseka D, Perry S, et al. Investigating unilateral pleural effusions: the role of cytology. Eur Respir J. 2018;52(5):1801254. Published Nov 8, 2018. DOI:10.1183/13993003.01254-2018
Ferrer J, Roldán J, Teixidor J, Pallisa E, Gich I, Morell F. Predictors of pleural malignancy in patients with pleural effusion undergoing thoracoscopy. Chest. 2005;127(3):1017-1022. DOI:10.1378/chest.127.3.1017
Corcoran JP, Acton L, Ahmed A, et al.: Diagnostic value of radiological imaging before and after drainage of pleural effusions. Respirology. February 2016;21(2):392-5. DOI:10.1111/resp.12675
Traill ZC, Davies RJ, Gleeson FV. Thoracic computed tomography in patients with suspected malignant pleural effusions. Clin Radiol. 2001;56(3):193-196. DOI:10.1053/crad.2000.0573
Hallifax RJ, Haris M, Corcoran JP, et al. Role of CT in assessing pleural malignancy prior to thoracoscopy. Thorax. 2015;70(2):192-193. DOI:10.1136/thoraxjnl-2014-206054
Villena V, López Encuentra A, Echave-Sustaeta J, Alvarez Martínez C, Martín Escribano P. Prospective study of 1,000 consecutive patients with pleural effusion. Etiology of the effusion and characteristics of the patients [Prospective study of 1,000 consecutive patients with pleural effusion. Etiology of the effusion and characteristics of the patients]. Arch Bronconeumol. 2002;38(1):21-26. DOI:10.1016/s0300-2896(02)75142-9
Syer T, Arnold DT, Patole S, et al. Investigation of a unilateral pleural effusion: What is the optimal CT scan coverage? Thorax. 2020;75(6):503-505. DOI:10.1136/thoraxjnl-2019-214309
Flores RM, Pass HI, Seshan VE, et al. Extrapleural pneumonectomy versus pleurectomy/decortication in the surgical management of malignant pleural mesothelioma: results in 663 patients. J Thorac Cardiovasc Surg 2008;135:620-626. DOI:10.1016/j.jtcvs.2007.10.054
Pass HI, Giroux D, Kennedy C et al. Supplementary prognostic variables for pleural mesothelioma: a report from the IASLC staging committee. J Thorac Oncol 2014;9:856-864. DOI:10.1097/JTO.0000000000000181
Kessler L, Schwaning F, Metzenmacher M et al. Fibroblast activation protein-directed imaging outperforms 18F-FDG PET/CT in malignant mesothelioma: a prospective, single-center, observational trial. J Nucl Med 2024;65:1188-1193. DOI:10.2967/jnumed.124.267473
Aigner C, Brüning T, Eberhardt WEE et al. Current treatment of asbestos-associated malignant pleural mesothelioma—An expert consensus paper (in German). Pneumologie 2021;75:776-794. DOI:10.1055/a-1404-1562
Hjerpe A, Abd Own S, Dobra K. An integrative approach to the cytologic and molecular diagnosis of malignant pleural mesothelioma. Transl Lung Canc Res 2020:9:934-943. DOI:10.21037/tlcr-2019-pps-10
Erasmus JJ, Truong MT, Smythe WR et al. Integrated computed tomography-positron emission tomography in patients with potentially resectable malignant pleural mesothelioma: Staging implications. J Thorac Cardiovasc Surg 2005;129:1364-1370. DOI:10.1016/j.jtcvs.2004.10.034
Plathow C, Staab A, Schmaehl A et al. Computed tomography, positron emission tomography, positron emission tomography/computed tomography, and magnetic resonance imaging for staging of limited pleural mesothelioma: initial results. Invest Radiol 2008;43:737-744. DOI:10.1097/RLI.0b013e3181817b3d
Sugarbaker DJ, Richards WG, Bueno R. Extrapleural pneumonectomy in the treatment of epithelioid malignant pleural mesothelioma: novel prognostic implications of combined N1 and N2 nodal involvement based on experience in 529 patients. Ann Surg 2014;260:577-580. DOI:10.1097/SLA.0000000000000903
Rice DC, Steliga MA, Stewart J et al. Endoscopic ultrasound-guided fine-needle aspiration for staging malignant pleural mesothelioma. Ann Thorac Surg 2009;88:862-868. DOI:10.1016/j.athoracsur.2009.05.022
Papotti M, Nicholson AG, Dacic S. Mesothelioma and Immunohistochemistry. In Yatabe Y, Borczuk AC, Cooper WA, et al (eds): IASLC Atlas of Diagnostic Immunohistochemistry, Denver, Colorado: IASLC 157–166, 2020.
Möhrmann L, Werner M, Olés M, et al. Comprehensive genomic and transcriptomic analysis enables molecularly guided therapy options in peritoneal and pleural mesothelioma. ESMO Open 2025;10:104532. DOI:10.1016/j.esmoop.2025.104532
Gill RR, Nowak AK, Giroux DJ et al. The International Association for the Study of Lung Cancer Mesothelioma Staging Project: Proposals for revisions of the “T” descriptors in the forthcoming ninth edition of the TNM classification for pleural mesothelioma. J Thorac Oncol 2024;19:1310-1325. DOI:10.1016/j.jtho.2024.03.007
Bille A, Ripley RT, Giroux DJ et al. The International Association for the Study of Lung Cancer Mesothelioma Staging Project: Proposals for the “N” descriptors in the forthcoming ninth edition of the TNM classification for pleural mesothelioma. J Thorac Oncol 2024;19:1326-1338. DOI:10.1016/j.jtho.2024.05.003
Kindler HL, Rosenthal A, Giroux DJ et al. The International Association for the Study of Lung Cancer Mesothelioma Staging Project: Proposals for the “M” descriptors in the forthcoming ninth edition of the TNM classification for pleural mesothelioma. J Thorac Oncol 2024;19:1564-1577. doi: 10.1016/j.jtho.2024.08.022.
Vogelzang NJ, Rusthoven JJ, Symanowski J et al. Phase III study of pemetrexed in combination with cisplatin versus cisplatin alone in patients with malignant pleural mesothelioma. J Clin Oncol 2003;21:2636-2644. DOI:10.1200/JCO.2003.11.136
de Perrot M, Feld R, Cho BC et al. Trimodality therapy with induction chemotherapy followed by extrapleural pneumonectomy and adjuvant high-dose hemithoracic radiation for malignant pleural mesothelioma. J Clin Oncol 2009;27:1413-1418. DOI:10.1200/JCO.2008.17.5604
Hasegawa S, Okada M, Tanaka F et al. Trimodality strategy for treating malignant pleural mesothelioma: results of a feasibility study of induction pemetrexed plus cisplatin followed by extrapleural pneumonectomy and postoperative hemithoracic radiation (Japan Mesothelioma Interest Group 0601 Trial). Int J Clin Oncol 2016;21:523-530. DOI:10.1007/s10147-015-0925-1
Katirtzoglou N, Gkiozos I, Makrilia N et al. Carboplatin plus pemetrexed as first-line treatment for patients with malignant pleural mesothelioma: a phase II study. Clin Lung Cancer 2010;11:30-35. DOI:10.3816/CLC.2010.n.005
Lim E, Waller D, Lau K et al. MARS 2 Investigators. Extended pleurectomy decortication and chemotherapy versus chemotherapy alone for pleural mesothelioma (MARS 2): a phase 3 randomized controlled trial. Lancet Respir Med 2024;12:457-466. DOI:10.1016/S2213-2600(24)00119-X
Grosso F, Cerbone L, Curioni-Fontecedro A. MARS 2 trial: the future of pleurectomy decortication in pleural mesothelioma. Lancet Respir Med 2024;12:423-424. DOI:10.1016/S2213-2600(24)00146-2
Lee M, Ventura L, Baranowski R, Hargrave J, Waller D. The Effects of Preserving the Diaphragm on Early and Late Outcomes of Lung-Sparing Radical Surgery for Malignant Pleural Mesothelioma. J Clin Med. 2022;11(22):6839. Published Nov 19, 2022. DOI:10.3390/jcm11226839
Breda C, Furia S, Lucchini G, et al. Long-term outcomes after lung-sparing surgery for epithelial mesothelioma. J Thorac Dis. 2021;13(11):6283-6293. DOI:10.21037/jtd-21-691
Raskin J, Surmont V, Maat APWM et al. A randomized phase II study of extended pleurectomy/decortication preceded or followed by chemotherapy in patients with early-stage pleural mesothelioma: EORTC 1205. Eur Respir J 2024;63:2302114. DOI:10.1183/13993003.02114-2023
Reuss JE, Lee PK, Mehran RJ et al. Perioperative nivolumab or nivolumab plus ipilimumab in resectable diffuse pleural mesothelioma: a phase 2 trial and ctDNA analyses. Nat Med 2025;31:4097-4108. DOI:10.1038/s41591-025-03958-3
Baas P, Scherpereel A, Nowak AK et al. First-line nivolumab plus ipilimumab in unresectable malignant pleural mesothelioma (CheckMate 743): a multicenter, randomized, open-label, phase 3 trial. Lancet 2021;397:375-386. DOI:10.1016/S0140-6736(20)32714-8
Popat S, et al: iMig Conference Presentation No. 370, 2021 .
Shah R, Buchmeier EL, Kopp HG, et al. First-line nivolumab plus ipilimumab in pleural mesothelioma: Efficacy and safety data from the real-world MesoNet study. Lung Cancer 2025 Sep;207:108702. DOI:10.1016/j.lungcan.2025.108702
Chu Q, Perrone F, Greillier L et al. Pembrolizumab plus chemotherapy versus chemotherapy in untreated advanced pleural mesothelioma in Canada, Italy, and France: a phase 3, open-label, randomized controlled trial. Lancet 2023;402:2295-2306. DOI:10.1016/S0140-6736(23)01613-6
Nowak AK, Forde PM, Brown C et al. Primary results of DREAM3R: Durvalumab (MEDI4736) with chemotherapy as first-line treatment in advanced pleural mesothelioma: a phase III randomized trial. Ann Oncol 2025;36(Supplement 2):S1646. DOI:10.1016/j.annonc.2025.09.121
Felip E, Popat S, Dafni U et al. A randomized phase III study of bevacizumab and carboplatin-pemetrexed chemotherapy with or without atezolizumab as first-line treatment for advanced pleural mesothelioma: results of the ETOP 13-18 BEAT-meso trial. Ann Oncol 2025;36:548-560. DOI:10.1016/j.annonc.2024.12.014
Szlosarek PW, Creelan BC, Sarkodie T et al. Pegargiminase plus first-line chemotherapy in patients with nonepithelioid pleural mesothelioma: the ATOMIC-Meso randomized clinical trial. JAMA Oncol 2024;10:475-483. DOI:10.1001/jamaoncol.2023.6789
https://www.ema.europa.eu/en/documents/orphan-designation/eu3141409-public-summary-opinion-orphan-designation-pegylated-recombinant-arginine-deiminase-treatment-malignant-mesothelioma_en
Dudek AZ, Wang X, Gu L et al. Randomized study of maintenance pemetrexed versus observation for the treatment of malignant pleural mesothelioma: CALGB 30901. Clin Lung Cancer 2020;21:553-561.e1. DOI:10.1016/j.ijsu.2020.09.052
de Gooijer CJ, van der Noort V, Stigt JA et al. Switch-maintenance gemcitabine after first-line chemotherapy in patients with malignant mesothelioma (NVALT19): an investigator-initiated, randomized, open-label, phase 2 trial. Lancet Respir Med 2021;9:585-592. DOI:10.1016/S2213-2600(20)30362-3
Bearz A, Talamini R, Rossoni G et al. Re-challenge with pemetrexed in advanced mesothelioma: A multi-institutional experience. BMC Res Notes 2012;5:482. DOI:10.1186/1756-0500-5-482
Zucali PA, Simonelli M, Michetti G et al. Second-line chemotherapy in malignant pleural mesothelioma: Results of a retrospective multicenter survey. Lung Cancer 2012;75:360-367. DOI:10.1016/j.lungcan.2011.08.011
Razak AR, Chatten KJ, Hughes AN. Retreatment with pemetrexed-based chemotherapy in malignant pleural mesothelioma (MPM): a second-line treatment option. Lung Cancer 2008;60:294-297. DOI:10.1016/j.lungcan.2007.08.031
Hayashi H, Okamoto I, Ichikawa Y et al. Retreatment of recurrent malignant pleural mesothelioma with cisplatin and pemetrexed. Int J Clin Oncol 2010;15:497-499. DOI:10.1007/s10147-010-0064-7
Ceresoli GL, Zucali PA, De Vincenzo F et al. Retreatment with pemetrexed-based chemotherapy in patients with malignant pleural mesothelioma. Lung Cancer 2011;72:73-77. DOI:10.1016/j.lungcan.2010.12.004
Zauderer MG, Kass SL, Woo K et al. Vinorelbine and gemcitabine as second- or third-line therapy for malignant pleural mesothelioma. Lung Cancer 2014;84:271-274. DOI:10.1016/j.lungcan.2014.03.006
Zucali PA, Perrino M, Lorenzi E et al. Vinorelbine in patients with malignant pleural mesothelioma who have previously received pemetrexed. Lung Cancer 2014;84:265-270. DOI:10.1016/j.lungcan.2013.11.011
Pinto C, Zucali PA, Pagano M et al. Gemcitabine with or without ramucirumab as second-line treatment for malignant pleural mesothelioma (RAMES): a randomized, double-blind, placebo-controlled, phase 2 trial. Lancet Oncol 2021;22:1438-1447. DOI:10.1016/S1470-2045(21)00404-6
Toyokawa G, Takenoyama M, Hirai F et al. Gemcitabine and vinorelbine as second-line or subsequent-line treatment in patients with malignant pleural mesothelioma who have previously received platinum-based plus pemetrexed chemotherapy. Int J Clin Oncol 2014;19:601-606. DOI:10.1007/s10147-013-0619-5
Fennell DA, Porter C, Lester J et al. Active symptom control with or without oral vinorelbine in patients with relapsed malignant pleural mesothelioma (VIM): a randomized, phase 2 trial. EClinicalMedicine 2022;48:101432. DOI:10.1016/j.eclinm.2022.101432
Popat S, Curioni-Fontecedro A, Dafni U et al. A multicenter randomized phase III trial comparing pembrolizumab versus single-agent chemotherapy for advanced, previously treated malignant pleural mesothelioma: the European Thoracic Oncology Platform (ETOP 9-15) PROMISE-meso trial. Ann Oncol 2020;31:1734-1745. DOI:10.1016/j.annonc.2020.09.009
Douma LH, Lalezari F, van der Noort V et al. Pembrolizumab plus lenvatinib in second-line and third-line patients with pleural mesothelioma (PEMMELA): a single-arm phase 2 study. Lancet Oncol 2023;24:1219-1228. DOI:10.1016/S1470-2045(23)00529-0
Vogelzang N, Taub R, Shin D. Phase III randomized trial of onconase (ONC) versus doxorubicin (DOX) in patients (Pts) with unresectable malignant mesothelioma (UMM): analysis of survival. Proc Am Soc Clin Oncol 2000:2274 .
Mikulski SM, Costanzi JJ, Vogelzang NJ et al. Phase II trial of a single weekly intravenous dose of ranpirnase in patients with unresectable malignant mesothelioma. J Clin Oncol 2002;20:274-281. DOI:10.1200/JCO.2002.20.1.274
Porta C, Paglino C, Mutti L. Ranpirnase and its potential for the treatment of unresectable malignant mesothelioma. Biologics 2008;2:601-609. DOI:10.2147/btt.s2383
Magri MD, Veronesi A, Foladore S et al. Epirubicin in the treatment of malignant mesothelioma: a phase II cooperative study. The North-Eastern Italian Oncology Group (GOCCNE)—Mesothelioma Committee. Tumori 1991;77:49-51. DOI:10.1177/030089169107700112
Mattson K, Giaccone G, Kirkpatrick A et al. Epirubicin in malignant mesothelioma: a phase II study of the European Organization for Research and Treatment of Cancer Lung Cancer Cooperative Group. J Clin Oncol 1992;10:824-828. DOI:10.1200/JCO.1992.10.5.824
Ceresoli GL, Aerts JG, Dziadziuszko R et al. Tumor Treating Fields in combination with pemetrexed and cisplatin or carboplatin as first-line treatment for unresectable malignant pleural mesothelioma (STELLAR): A multicenter, single-arm phase 2 trial. Lancet Oncol 2019;20:1702-1709. DOI:10.1016/S1470-2045(19)30532-7
Jenkins P, Milliner R, Salmon C. Re-evaluating the role of palliative radiation therapy in malignant pleural mesothelioma. Eur J Cancer 2011;47:2143-2149. DOI:10.1016/j.ejca.2011.05.012
MacLeod N, Chalmers A, O'Rourke N et al. Is Radiotherapy Useful for Treating Pain in Mesothelioma?: A Phase II Trial. J Thorac Oncol 2015;10:944-950. DOI:10.1097/JTO.0000000000000499
Fodor A, Fiorino C, Dell'Oca I et al. PET-guided dose escalation tomotherapy in malignant pleural mesothelioma. Radiother Oncol 2011;187:736-743. DOI:10.1007/s00066-011-2234-6
Harling L, Kolokotroni SM, Nair A et al. Differential survival characteristics of the sarcomatoid subtype in biphasic pleural mesothelioma. Ann Thorac Surg 2019;107:929-935. DOI:10.1016/j.athoracsur.2018.09.019
Schröder C, Opitz I, Guckenberger M et al. Stereotactic body radiation therapy (SBRT) as salvage therapy for oligorecurrent pleural mesothelioma after multimodal therapy. Front Oncol 2019;26;9:961. DOI:10.3389/fonc.2019.00961
Ghirardelli P, Franceschini D, D'Aveni A et al. Salvage radiotherapy for oligo-progressive malignant pleural mesothelioma. Lung Cancer 2021:152:1-6. DOI:10.1016/j.lungcan.2020.11.022
Rimner A, Zauderer MG, Gomez DR et al. Phase II study of hemithoracic intensity-modulated pleural radiation therapy (IMPRINT) as part of lung-sparing multimodality therapy in patients with malignant pleural mesothelioma. J Clin Oncol 2016;34:2761-2768. DOI:10.1200/JCO.2016.67.2675
Trovo M, Relevant A, Polesel J et al. Radical hemithoracic radiotherapy versus palliative radiotherapy in non-metastatic malignant pleural mesothelioma: results from a phase 3 randomized clinical trial. Int J Radiat Oncol Biol Phys 2021;109:1368-1376. DOI:10.1016/j.ijrobp.2020.11.057
Cho BCJ, Donahoe L, Bradbury PA et al. Surgery for malignant pleural mesothelioma after radiotherapy (SMART): final results from a single-center, phase 2 trial. Lancet Oncol 2021;22:190-197. DOI:10.1016/S1470-2045(20)30606-9
Zalcman G, Mazieres J, Margery J et al. French Cooperative Thoracic Intergroup (IFCT): Bevacizumab for newly diagnosed pleural mesothelioma in the Mesothelioma Avastin Cisplatin Pemetrexed Study (MAPS): a randomized, controlled, open-label, phase 3 trial. Lancet 2016;387:1405-1414. DOI:10.1016/S0140-6736(15)01238-6
Lauk O, Bruestle K, Neuer T et al. The impact on outcome of adding bevacizumab to standard induction chemotherapy prior to mesothelioma surgery: a retrospective single-center analysis. Front Oncol 2020;10:588563. DOI:10.3389/fonc.2020.588563
10Active Studies / Registries
11Systemic Therapy - Protocols
12Study Results
13Systemic drugs - approval status
14Links
16Disclosure of Potential Conflicts of Interest
according to the rules of the responsible Medical Societies.
Download
Reference:
Quellenangabe:
Onkopedia-Leitlinien werden kontinuierlich an den Stand des Wissens angepasst. Die jeweils gültige Version, AGB und Nutzungsbedingungen finden Sie unter www.onkopedia.com.
Für die kommerzielle Nutzung wenden Sie sich bitte an onkopedia@dgho.de.
Onkopedia guidelines are continuously adapted to the state of knowledge. The currently valid version, terms of use and general terms and conditions can be found at onkopedia-guidelines.info.
For commercial use, please contact onkopedia@dgho.de.
